

When Responsibility Becomes Anxiety: Perinatal OCD in High-Achieving Mothers
Women accustomed to being prepared and solving problems may find motherhood's uncertainty particularly difficult. Amber Morris, PsyD, PMH-C, explores how responsibility, perfectionism, and the need for certainty can contribute to perinatal OCD and anxiety.

During my years as a psychologist in the Navy, I worked in environments where preparation, attention to detail, and anticipating risk were essential. In high-stakes settings, these qualities can be incredibly valuable. You learn to identify potential problems, prepare for different outcomes, and take your responsibilities seriously. Working with military mothers taught me something about what can happen when those same instincts are brought into motherhood.
I began to see how difficult it can be for a woman who is used to being prepared and competent to enter a role where no amount of preparation can guarantee that everything will be okay. I now recognize this same pattern in many of the women I work with—physicians, attorneys, executives, academics, entrepreneurs, and other highly responsible women who are accustomed to being the person others rely on. They may have spent years building successful careers, making difficult decisions, and solving complicated problems. They are thoughtful, conscientious, and deeply invested in doing things well.
Then they become mothers, and suddenly there are endless decisions to make and an enormous amount of uncertainty that cannot be solved through better preparation. Am I feeding the baby enough? Was that medication safe during pregnancy? What if I missed something? What if something happens and I don't know about it? What if I'm not doing this right?
For some women, the desire to be a good mother gradually becomes a feeling that they need to do everything perfectly in order to keep their baby safe. The standards they have used to succeed in other areas of their lives can become impossible standards for motherhood. This is where perinatal anxiety and OCD can take hold.
When Being Responsible Starts to Feel Like Being Vigilant
Some degree of vigilance is a normal part of becoming a parent. New parents check on their babies, research questions, and pay close attention to changes in feeding, sleep, development, and health. The problem isn't caring about your baby too much. The problem is when anxiety convinces you that being a good mother means staying one step ahead of every possible danger.
For a woman experiencing perinatal anxiety or OCD, this might look like repeatedly checking the baby monitor, researching a symptom late into the night, asking a partner or pediatrician for reassurance, or going over the same decision again and again because she cannot feel completely certain that she made the right one. It may look like reading every available source about a medication during pregnancy, repeatedly checking whether something is safe for breastfeeding, or feeling unable to make an ordinary parenting decision without first consulting multiple sources.
At first, these behaviors can feel like responsible parenting. I'm just being careful. I'm just making sure. I just want to know that everything is okay.
But eventually, the goal can shift from being informed to feeling certain. And certainty is something anxiety and OCD can keep moving further away.
This can be particularly confusing for high-achieving women because the strategies that are driving the anxiety may be the same strategies that have worked extremely well for them everywhere else. Researching, preparing, anticipating problems, and seeking more information have probably helped them make good decisions throughout their lives. It can be difficult to recognize when those same strengths have crossed over into a cycle that is no longer helping.
Checking and Reassurance Seeking
A mother might check that her baby is breathing repeatedly throughout the night. She might inspect bottles or feeding equipment over and over, repeatedly ask her partner whether the baby feels too warm, or spend hours searching online for information about a symptom. She may know that she has already received reassurance, but still feel compelled to ask again.
The problem isn't the information itself. It is the belief that one more check, one more search, or one more question will finally make the uncertainty go away. For someone who is accustomed to solving problems through preparation and information, this can be a particularly convincing trap.
Over time, the questions may become increasingly specific. Was that cough normal? What if it means something more serious? What if the pediatrician missed something? What if I didn't explain the symptoms correctly? The mother may recognize that she is asking the same question in different forms, but still feel unable to stop until she feels completely reassured.
Unfortunately, complete reassurance rarely lasts.
Intrusive “What If” Thoughts
Perinatal OCD can also involve sudden, unwanted thoughts or images about something terrible happening to your baby. A mother might have an intrusive thought about dropping the baby down the stairs, someone hitting their car, the baby dying in their sleep, or accidentally hurting the baby herself.
These thoughts can be especially frightening because they often feel completely inconsistent with what a mother wants. She may start wondering why she had the thought in the first place or what it says about her that her brain produced it. Would I really have this thought if I were a good mother? Why can I picture this so clearly? What if having the thought means something about me?
An intrusive thought is not an intention or a prediction, and having a disturbing thought does not mean you want it to happen. In fact, OCD often targets the things we care about most.
The difficulty comes when the thought is interpreted as meaningful or dangerous and the mother begins trying to prevent, neutralize, or gain certainty about it. She may start monitoring herself more closely, avoiding situations that trigger the thought, seeking reassurance that she would never act on it, or mentally reviewing what happened to make sure she is a good and safe mother.
Avoidance and Mental Rituals
Not every compulsion is visible. A mother might avoid carrying her baby down the stairs because she is afraid of having an intrusive thought, avoid driving with her baby, or feel unable to be alone with the baby. She might repeatedly replay the day in her mind, trying to determine whether she said or did something that could have caused harm.
These behaviors can be difficult to recognize as compulsions because they can look like caution or responsibility. But if the goal is to eliminate uncertainty or make absolutely certain that nothing bad will happen, they can become part of the OCD cycle.
Sometimes the mental rituals are even harder to identify. A mother may spend hours analyzing whether she felt the “right” amount of love when she looked at her baby, reviewing whether she responded appropriately to a crying infant, or mentally comparing her experience of motherhood to what she thinks other mothers are feeling. The content can change, but the underlying question remains the same: Can I know for certain that I am doing this right?
When Preparation Can't Solve Uncertainty
One of the things my military experience taught me is that preparation can be incredibly adaptive. Checklists, contingency plans, repetition, and attention to detail can help people function effectively in high-stakes environments. But motherhood introduces a kind of uncertainty that preparation cannot eliminate.
You can follow every recommendation and your baby can still get sick. You can make a careful decision and later wonder if another decision would have been better. You can research the safest car seat, follow every sleep recommendation, choose the healthiest foods, and do everything you reasonably can to protect your child—and still not be able to guarantee what happens next.
For someone who has spent years being rewarded for being prepared, responsible, and capable, that can be incredibly uncomfortable. When uncertainty feels intolerable, trying harder can feel like the obvious solution. So you research a little more, check one more time, ask your partner, call the pediatrician, or replay what happened in your mind. You try to make sure.
The problem is that the relief that comes from checking or reassurance can actually strengthen the cycle. Your brain learns that the anxiety required a response—that the threat must have been important because you took action to neutralize it. Over time, the goal can become less about caring for your baby and more about getting rid of the feeling that something might be wrong.
This is one reason perinatal OCD can be so difficult for highly responsible women to recognize in themselves. The behaviors can look like conscientiousness from the outside. From the inside, they can feel like the only responsible thing to do.
From “Perfect” to “Good Enough”
Treatment for perinatal anxiety and OCD isn't about becoming careless or ignoring legitimate concerns. It isn't about convincing yourself that nothing bad will ever happen, and it isn't about eliminating every scary thought. Instead, treatment involves learning to respond differently to uncertainty and intrusive thoughts.
Part of that process is learning to recognize intrusive thoughts for what they are. An unwanted thought or image is not an intention, prediction, or reflection of your character. You don't have to figure out why you had the thought or prove that you would never act on it.
It also involves learning to distinguish care from compulsion. Checking, researching, and asking questions can all be reasonable parts of parenting. The question is what function they are serving. Are you gathering information you genuinely need, or are you trying to reach a level of certainty that isn't possible?
For many women, this means learning to tolerate the discomfort of not knowing. You may not know with absolute certainty that your baby is okay. You may not know that you made the perfect parenting decision. You may not know that an intrusive thought will never return. Recovery involves learning that you can experience that uncertainty without responding to it with another check, search, question, avoidance behavior, or mental review.
And perhaps most importantly, you can begin to let “good enough” actually be enough. Being a good mother does not require constant vigilance. It does not require perfect decisions, and it does not require you to eliminate every possible risk.
You Don't Have to Be Certain to Be a Good Mother
One of the things I have learned through my work with mothers is that strength and anxiety can coexist. You can be highly capable and still struggle with OCD. You can be exceptionally responsible and still find yourself Googling your baby's symptoms at 2 a.m. You can know intellectually that an intrusive thought doesn't make sense and still feel terrified by it. And you can love your baby deeply without being able to guarantee their safety.
Motherhood asks us to tolerate something that can be particularly difficult for people who are accustomed to being competent and prepared: uncertainty. The goal isn't to care less. It is to learn that you can care deeply for your child without having to live in a constant state of alarm.
If you find yourself caught in cycles of checking, reassurance seeking, researching, avoidance, or trying to control every possible risk, perinatal anxiety and OCD are highly treatable. Working with a clinician who understands both the perinatal transition and the specific ways OCD can show up during pregnancy and early parenthood can help you step out of the cycle without asking you to become a less caring or less responsible mother.
Amber Morris, PsyD, PMH-C
Clinical Psychologist | Red Elm Psychotherapy
Amber Morris, PsyD, PMH-C, is a clinical psychologist specializing in perinatal OCD, intrusive thoughts, anxiety, and trauma during pregnancy, postpartum, and early parenthood. She provides evidence-based treatment, including Exposure and Response Prevention (ERP) for OCD and Prolonged Exposure (PE) for PTSD.
Drawing on her experience as an active-duty Navy psychologist and her work in military and medical settings, Amber understands the unique challenges that pregnancy, parenthood, and major life transitions can bring. Her approach is warm, direct, and collaborative, helping clients navigate intrusive thoughts, reduce compulsive patterns, and build greater flexibility in the face of uncertainty.
Amber earned her doctorate in clinical psychology from Wright State University and is a Certified Perinatal Mental Health Professional (PMH-C) through Postpartum Support International. She provides telehealth services to clients in Virginia and participating PSYPACT states.

The “ERP Lite” Trap: When Safety Behaviors Undermine Exposure and Response Prevention
You can be doing ERP and still accidentally keep OCD going. Learn how subtle safety behaviors can interfere with response prevention—and how to recognize “ERP Lite” in your own exposures.
By Dr. Niles Cook, Psy.D. — Red Elm Psychotherapy
If you have been working through Exposure and Response Prevention (ERP) for Obsessive-Compulsive Disorder (OCD), you already know the core premise: to overcome anxiety, you have to face the things that trigger it. You lean into the discomfort, step toward the uncertainty, and allow your brain to learn something new.
In our previous posts, "Why ERP Feels So Wrong" and "Why Insight Isn't Enough," we explored why logical understanding alone cannot quiet an anxious brain and why true exposure often flies in the face of our basic survival instincts.
However, many people encounter a frustrating plateau mid-treatment: they are actively confronting their triggers, yet their baseline anxiety and intrusive thoughts remain as intense as ever.
When this happens, the culprit is often "ERP Lite"—the practice of completing physical exposures while quietly keeping safety behaviors and mental compulsions intact.
Importantly, "ERP Lite" doesn't mean you have failed at ERP. Safety behaviors are often subtle and can be difficult to recognize, especially early in treatment. Identifying them is part of the learning process.
What Is "ERP Lite"?
ERP Lite occurs when you perform the Exposure (E) half of the equation but quietly bypass or dilute the Response Prevention (RP) half.
It feels like you are doing the hard work because you are putting yourself in trigger-rich environments. But under the surface, your brain is relying on subtle safety behaviors to cushion the blow.
The "ERP Lite" Cycle:
Exposure (Trigger): You face the situation or thought that provokes distress.
Subtle Safety Behavior: You use a mental mantra, self-soothing talk, or micro-avoidance to soften the anxiety.
Brain's Conclusion: "We survived ONLY because we used that safety behavior."
Result: The OCD threat signal remains intact, potentially limiting the learning that effective response prevention is intended to promote.
Because your brain may attribute your ability to tolerate the exposure to the safety behavior—not your natural capacity for emotional tolerance—the underlying threat signal can remain active.
4 Subtle Safety Behaviors That Can Neutralize Exposure
Safety behaviors can be notoriously difficult to spot because they often masquerade as "mindfulness," "positive self-talk," or standard therapeutic techniques.
1. The Internal Mantra (Self-Soothing During the Trigger)
What it looks like: Repeating phrases like "I am safe," "This is just my OCD," or "Nothing bad will happen" continuously while touching a contaminated surface or leaning into a feared scenario.
Why it can sabotage progress: Effective response prevention means practicing not using compulsions or avoidance to resolve the uncertainty created by the obsession. Using reassuring mantras can turn self-talk into a covert mental compulsion designed to lower distress in real time.
2. Performing Exposures to "Prove" a Fear False
What it looks like: Leaving a light switch unchecked specifically to prove to yourself that the house won't catch fire, then constantly monitoring news alerts or listening for fire engines in the background.
Why it can sabotage progress: ERP is not a scientific test designed to prove your core fear false; it is an exercise in tolerating the possibility of uncertainty. When you enter an exposure with the rigid expectation of a safe outcome, you can maintain your obsession with certainty.
3. Immediate Post-Exposure Neutralization
What it looks like: Holding a knife or sitting with an intrusive thought for 10 minutes, but immediately going into a deep mental review, reassurance search, or physical cleaning cycle as soon as the timer ends.
Why it can sabotage progress: Treating response prevention like a timed test misses the point. Delaying a compulsion only to execute it a few minutes later can reinforce the idea that the exposure was dangerous and required eventual cleanup.
4. Selective "Micro-Avoidance"
What it looks like: Sitting on a public couch without wiping it down, but keeping your arms tightly crossed so your sleeves never touch the fabric.
Why it can sabotage progress: These micro-adjustments act as psychological release valves. They keep your arousal levels manageable in the moment, but they can interfere with the inhibitory learning ERP is designed to promote—the process through which you learn that you can tolerate uncertainty without relying on a safety behavior.
Standard ERP vs. "ERP Lite"
| Full ERP / Response Prevention | “ERP Lite” |
|---|---|
| Face the trigger while practicing response prevention | Face the trigger while retaining safety behaviors |
| Allow uncertainty rather than seeking reassurance | Use reassurance or mental strategies to feel safer |
| Resist compulsions during and after the exposure | Delay compulsions or neutralize afterward |
| Focus on changing your response to uncertainty | Focus on proving the feared outcome will not happen |
| Supports new learning and greater flexibility | Can maintain the OCD cycle |
How to Shift from "ERP Lite" to Full Response Prevention
If you recognize these subtle safety behaviors in your practice, do not be discouraged—identifying them is often the exact turning point in treatment.
1. Audit Your Exposures for "Safety Buffers"
Before starting an exposure, ask yourself: "What am I doing right now to make this feel manageable?"
If the answer involves a mental chant, body positioning, or reassurance, you don't have to eliminate it all at once. Bring it to your therapist and begin experimenting with what happens when you gradually rely on that buffer less.
2. Shift the Goal to Uncertainty
Replace "I want my distress score to drop" with "I want to practice sitting with 'maybe/maybe not'."
3. Extend Response Prevention Beyond the Exercise
Treat response prevention as an all-day mindset rather than a brief drill. If an urge to check or neutralize arises 30 minutes after an exposure, apply response prevention right then.
Remember, ERP does not require you to stay anxious or prevent yourself from ever feeling better. The goal is to practice responding differently to obsessions and uncertainty rather than relying on compulsions or avoidance to make the anxiety go away.
Download Your Self-Audit Worksheet
Want to pinpoint the hidden safety behaviors that might be slowing down your ERP progress? Download our free Safety Behavior & Response Prevention Self-Audit Worksheet from Red Elm Psychotherapy to audit your exposures and track micro-compulsions.
Specialized ERP Therapy in Virginia
Navigating subtle mental compulsions and safety behaviors often requires an experienced specialist who can help you identify micro-avoidance patterns that pass under the radar.
Dr. Niles Cook offers specialized Exposure and Response Prevention (ERP) therapy tailored to your specific OCD themes in Vienna, VA, and virtually throughout Virginia and PSYPACT-participating states. Whether you are starting treatment for the first time or trying to break through a plateau, targeted guidance can help you move from "ERP Lite" toward lasting recovery.

Can OCD Make It Harder to Get Pregnant?
If you have OCD and are trying to conceive, you may wonder whether your anxiety, intrusive thoughts, or something you've done is making it harder to get pregnant. Learn how OCD can turn fertility into a cycle of checking, researching, reassurance seeking, and trying to control the outcome.
If you have Obsessive Compulsive Disorder (OCD) and are trying to conceive, you may find yourself wondering whether your OCD is somehow getting in the way of becoming pregnant. Maybe you worry that stress is affecting your fertility, that your thoughts are somehow interfering with conception, or that something you ate, drank, did, or failed to do has made pregnancy less likely.
Having OCD does not mean that you cannot get pregnant. OCD is not the same thing as infertility, and having intrusive thoughts does not cause infertility.
What can happen, however, is that trying to conceive can become a particularly powerful trigger for OCD. There is so much you cannot know. You don't know exactly when you'll get pregnant, whether this will be the month, whether something you did affected your chances, or whether there is something else you should be doing. For someone with OCD, that uncertainty can create a powerful urge to check, research, monitor, and seek reassurance.
You might find yourself repeatedly tracking ovulation, researching ways to increase your chances of conceiving, taking pregnancy tests earlier or more frequently than you intended, or searching for signs that implantation has occurred. You might replay something you ate or drank and wonder whether it could have affected your chances. You might avoid activities because you're afraid they could interfere with conception, feel compelled to have sex at exactly the “right” time, or spend a significant amount of time trying to determine whether you're doing everything possible to get pregnant.
These behaviors can make trying to conceive feel all-consuming. And because compulsions often provide temporary relief, it can be difficult to recognize when something that initially seemed helpful has become part of the OCD cycle.
When Trying to Get Pregnant Becomes Trying to Get Certainty
No one likes working toward something without knowing whether or not it will work out. Your OCD really doesn't like it.
Trying to conceive can involve an enormous amount of waiting and uncertainty. You may know when you ovulated, but you don't know whether conception occurred. You may know when you can take a pregnancy test, but you don't know what the result will be. And if you don't become pregnant this month, you may find yourself starting the process all over again.
For someone with OCD, that uncertainty can quickly turn into questions that feel as though they need to be answered.
What if I miss my fertile window?
What if I did something wrong?
What if I should have done something differently?
What if this happens again next month?
These questions may not simply come and go. They can start to feel like problems that need to be solved. And once OCD decides there is a problem, it offers a familiar solution: get more information, check one more thing, ask someone who might know, or find some way to make sure you haven't missed anything.
So you track your cycle more carefully. You research supplements. You monitor physical sensations. You ask your doctor another question. You look through online forums to see whether other women experienced the same thing. You take a pregnancy test as soon as it could possibly tell you anything.
And for a little while, these things may actually make you feel better.
The problem is that the relief doesn't last. Soon there is another question.
But what if I tested too early?
What if I miscalculated when I ovulated?
What if that symptom means something else?
What if I didn't do enough?
So you check again.
This is the OCD cycle: the very behaviors intended to make uncertainty more manageable can ultimately make uncertainty feel more threatening.
When “Doing Everything Right” Becomes the Problem
Trying to conceive comes with no shortage of advice. Eat this. Don't eat that. Take this supplement. Avoid that activity. Track your temperature. Watch for ovulation. Have sex on this day. Don't miss this window.
Some of this information may be useful. You may reasonably decide that certain changes are worth making, particularly when they are recommended by your medical provider. The problem isn't taking care of your fertility. The problem is when OCD turns reasonable care into a demand for perfection.
You may start with a question like, What might help? But OCD can quickly turn that into, What if I don't do everything perfectly?
Then suddenly you're not just trying to conceive. You're trying to eliminate every possible reason pregnancy might not happen.
You might research one more supplement, change your exercise routine, eliminate another food, recalculate when you ovulated, search for implantation symptoms, or look for reassurance that something you did three days ago hasn't reduced your chances of becoming pregnant.
And sometimes the behavior itself looks completely reasonable. That's part of what makes OCD around fertility so difficult to recognize.
Tracking ovulation isn't inherently a compulsion. Asking your doctor a question isn't inherently reassurance seeking. Taking a prenatal vitamin isn't a compulsion. Even doing quite a bit of fertility research isn't necessarily a problem.
The more useful question is what happens after you do those things.
Can you take the information and move on? Or does OCD immediately ask another question?
But what if I missed something?
What if I should be doing more?
What if that wasn't enough?
There is an important difference between making an informed choice and trying to reach a level of certainty that doesn't actually exist.
When Fertility Becomes Something You Feel Responsible for Controlling
One of the hardest parts of OCD around conception can be the feeling that if you just do enough, you can make the outcome happen.
If you eat perfectly, take every supplement, exercise the right amount, have sex at exactly the right time, manage your stress, get enough sleep, avoid anything potentially harmful, and do everything correctly, maybe you can make sure you get pregnant.
And if you don't?
It can be very easy to turn that uncertainty back on yourself.
What did I do wrong?
What did I miss?
Maybe I should have known.
Maybe I didn't try hard enough.
For someone with OCD, this can become especially painful because it creates the illusion that the outcome is entirely your responsibility. If you could just identify the missing variable, perhaps you could finally make pregnancy happen.
But fertility doesn't work that way. There are many things you can reasonably do to support your fertility, and there are many situations in which medical care can help. None of that means you can completely control whether or when you become pregnant.
That distinction can be incredibly difficult for OCD to tolerate.
What If There Really Is a Fertility Problem?
This is where things can get complicated, because sometimes there really is a medical problem to address.
You may have been trying to conceive for a while. Your doctor may recommend testing. You may be pursuing fertility treatment. You may have unexplained infertility. OCD doesn't mean those concerns aren't real.
You don't need to avoid fertility testing or pretend that everything is fine in order to treat OCD. You can follow your doctor's recommendations and still have OCD. You can ask an appropriate question and still have OCD. You can make a thoughtful decision about fertility treatment and still have OCD.
The difficulty is that getting information and getting reassurance can look remarkably similar from the outside.
You may ask your doctor a reasonable question. Then you ask your partner. Then you search online. Then you find another study. Then you call your doctor again because you're still not completely sure.
The information itself may be legitimate. But if you're repeatedly seeking information because you're waiting for the feeling of certainty to arrive, you may find yourself caught in the OCD cycle.
There is a difference between getting the information you need and trying to get information that will finally make you certain.
This can be especially difficult when you're pursuing fertility treatment because there are real decisions to make and legitimate reasons to want more information. At the same time, OCD may continue asking questions that medicine simply cannot answer with certainty.
What if this treatment doesn't work?
What if we should try something else?
What if I make the wrong decision?
What if I don't do enough?
At some point, the work may be recognizing, I've gotten the information I reasonably can. Now I have to make a decision and live with some uncertainty.
That's not the same thing as giving up or failing to advocate for yourself. It's recognizing the point at which further information is no longer helping you make a decision and is instead becoming another attempt to feel certain.
What About the Fear That Stress Is Preventing Pregnancy?
Another particularly difficult OCD trap is the fear that your own anxiety is causing the problem.
You may have heard that stress affects the body or read that stress can affect fertility. Then OCD can take that information and turn it into another impossible responsibility.
What if my anxiety is preventing me from getting pregnant?
What if I'm too stressed?
What if worrying about getting pregnant is making it harder to get pregnant?
Now you have a new problem: you need to stop being anxious in order to get pregnant.
And trying desperately not to be anxious tends to make you more aware of your anxiety. You start monitoring how stressed you are, judging yourself for feeling anxious, and worrying that the fact that you're worrying is making things worse.
I've worked with women who become caught in exactly this kind of loop. They aren't only worried about whether they'll get pregnant; they're worried that they're responding to the possibility of not getting pregnant incorrectly, and that their response itself is somehow making the situation worse.
You don't need to achieve some perfectly calm emotional state before you're allowed to try to conceive. And you don't need to stop having intrusive thoughts in order for conception to happen.
Trying to eliminate every anxious thought can simply become another way of trying to control an outcome that cannot be completely controlled.
Learning to Try Without Trying to Control Everything
Treating OCD while trying to conceive isn't about convincing yourself that fertility doesn't matter or telling yourself that you shouldn't care so much.
You can take your prenatal vitamin. You can track ovulation if that's useful to you. You can follow your doctor's recommendations. You can pursue fertility testing or treatment when appropriate. You can make thoughtful decisions about your health.
And you can still have OCD.
The work is learning to recognize when reasonable fertility care has crossed over into an attempt to eliminate uncertainty.
That might mean noticing the urge to search one more time and choosing not to. It might mean taking an ovulation test without then spending an hour researching what the result means. It might mean allowing yourself to wonder whether this month will be the month without trying to figure out every possible variable. It might mean having a thought like What if I did something that prevented this from working? and resisting the urge to go back through the last several days looking for an answer.
Sometimes it means allowing yourself to say, I don't know.
I don't know whether this month will work.
I don't know exactly when I'll get pregnant.
I don't know whether I could have done something differently.
I don't know whether everything will happen the way I hope.
And I don't have to solve those questions right now.
OCD Treatment While Trying to Conceive
Treatment for OCD during this stage of life isn't about convincing yourself that everything will work out. It's about learning that you can experience uncertainty without needing to solve it.
Evidence-based OCD treatment such as Exposure and Response Prevention (ERP) can help you practice experiencing uncertainty without responding with the compulsions that temporarily make you feel safer. Acceptance and Commitment Therapy (ACT) can also help you make room for difficult thoughts and feelings without allowing them to dictate what you do.
For women trying to conceive, treatment may focus specifically on the situations that have become difficult: fertility testing, ovulation tracking, sex and timing, pregnancy testing, researching fertility, physical sensations, medical appointments, or the uncertainty of whether conception will happen.
You don't have to care less about becoming a mother. You don't have to stop hoping that this will be the month. And you don't have to give up on appropriate fertility care.
You can want this very badly and still learn not to let OCD run the process.
Fertility OCD Therapy
If trying to conceive has started to feel like something you have to monitor, research, control, or get exactly right, you may be dealing with more than ordinary fertility anxiety.
You don't have to wait until OCD is taking hours out of your day or interfering with your relationships to get help. And you don't have to choose between taking your fertility seriously and treating OCD.
At Red Elm Psychotherapy, we specialize in OCD and perinatal mental health, including OCD that shows up while trying to conceive, during fertility treatment, and throughout pregnancy. Our approach incorporates Exposure and Response Prevention (ERP), Acceptance and Commitment Therapy (ACT), and other evidence-based treatments for OCD.
Treatment can help you learn to distinguish between reasonable fertility care and compulsive attempts to eliminate uncertainty, so you can make informed decisions about your fertility without feeling like you have to control every variable.
If you're spending more and more time checking, researching, seeking reassurance, or worrying that you've done something to prevent pregnancy, you don't have to figure this out on your own.
Or, if you're ready to talk with someone about whether therapy might be a good fit, contact Red Elm Psychotherapy to get started below.

Everyone Gets Intrusive Thoughts. Why Does OCD Feel So Different?
Intrusive thoughts are a normal part of being human. So why can the same thought feel completely different when OCD gets involved? Learn how OCD changes the way we respond to unwanted thoughts, uncertainty, and “what if?” questions.
Have you ever been standing on a high balcony and suddenly thought, “What if I jumped?” Or turned off your stove, left the house, and immediately wondered, “What if the house catches fire?”
If so, you’ve experienced an intrusive thought—a sudden, unwanted idea, mental image, or urge that pops into your mind without being intentionally invited.
Here is the surprising reality: intrusive thoughts are extremely common. Research suggests that the vast majority of people experience strange, random, or alarming intrusive thoughts at some point.
So why do these thoughts pass harmlessly through one person’s mind, while completely hijacking another person’s day?
The key lies in understanding the difference between everyday anxiety, everyday intrusive thoughts, and OCD-driven intrusive thoughts.
More specifically, the difference often isn't the thought itself.
It is what happens next.
What Are Intrusive Thoughts, Really?
At its core, the human brain is a perpetual content generator. It produces thoughts, images, memories, predictions, and associations all day long—some useful, some creative, and many completely bizarre.
Intrusive thoughts are simply thoughts that enter your awareness without your choosing them, often in ways that feel strange, disturbing, or completely out of character.
For most people, these thoughts are treated like spam mail: annoying or nonsensical, but ultimately unimportant. The thought appears, perhaps creates a moment of discomfort, and then the brain moves on.
When anxiety or Obsessive Compulsive Disorder (OCD) enters the picture, however, the brain can begin treating certain thoughts as important signals that require attention.
The brain's threat-detection and learning systems are designed to notice potential danger and help us respond to things that seem important. With OCD, that system can become overly focused on a particular thought, possibility, or uncertainty.
A thought that could otherwise disappear into the background suddenly feels like something that needs to be figured out, prevented, checked, or resolved. What begins as a single intrusive thought can then become part of the OCD cycle: the thought triggers a sense of threat, the person responds by trying to find certainty or reduce the discomfort, and the temporary relief can make the thought feel even more important the next time it appears.
And that's where the trouble begins.
Comparing the Three: Anxious, Everyday Intrusive, and OCD Thoughts
To see how OCD can fundamentally change the way a thought is experienced, consider how different mindsets process the exact same life scenarios.
Scenario A: Driving on the Highway
1. Everyday Anxiety Thought:
"Traffic is moving fast and the weather is worsening. I hope I don't get into an accident."
Processing: You feel a steady, manageable pulse of worry. It causes you to slow down, grip the steering wheel slightly tighter, or turn off the radio to focus.
Mechanism: Context-driven and problem-oriented. The worry is connected to a real-world situation, and your response serves a practical function.
2. Everyday Intrusive Thought:
"What if I swerved into oncoming traffic right now?"
Processing: A momentary flash of discomfort or confusion. You recognize the thought as bizarre or unwanted, dismiss it within seconds, and keep your hands steady on the wheel.
Mechanism: Unwanted, but ultimately unimportant. The thought doesn't align with your intentions, and your brain allows it to fade naturally.
3. OCD Intrusive Thought:
"I had a passing thought about swerving. What if that means I secretly want to harm someone? What if I could lose control for a split second and hit someone without realizing it?"
Processing: A visceral wave of dread. You may suddenly feel an urge to replay the last few minutes in your head, check your rear-view mirror repeatedly, monitor yourself for signs that you might lose control, pull over, seek reassurance, or avoid driving altogether.
Mechanism: Threat-amplified and sticky. The mind treats a harmless mental spark as a severe moral or physical emergency that requires immediate resolution.
The thought itself isn't necessarily different.
The meaning assigned to the thought—and the response that follows—can be dramatically different.
Scenario B: Leaving the House
1. Everyday Anxiety Thought:
"I'm running late, and I have so much on my mind. I hope I didn't forget to lock up properly."
Processing: Stress revolves around your busy schedule and real-life consequences. You double-check the lock if you're genuinely unsure, feel slightly frustrated by your rush, and move on.
Mechanism: Context-driven worry. The concern is connected to an actual task and can be resolved without requiring absolute certainty.
2. Everyday Intrusive Thought:
"Did I unplug the iron?"
Processing: You pause for a second, recall turning it off, or decide to take a quick peek before walking out the door. Once you've checked, the matter is closed.
Mechanism: Simple mental query. A quick cognitive check that resolves smoothly.
3. OCD Intrusive Thought:
"If the door isn't locked in the precise right way, an intruder will break in, and it will be entirely my fault. I must make sure."
Processing: Intense bodily tension, heart racing, and a sense that safety is entirely compromised unless a strict, absolute condition is met.
You check the lock.
Then you wonder whether you checked it correctly.
So you check again.
Maybe you take a picture. Ask someone else to verify it. Drive back home. Or spend the next hour mentally replaying whether you actually locked it.
Mechanism: Catastrophic and absolute. The thought converts uncertainty into an emergency and creates a powerful demand for certainty.
The Difference Is Often What Happens Next
This is one of the most important distinctions to understand about OCD.
People with OCD do not necessarily have completely different intrusive thoughts from everyone else.
The difference is often what happens after the thought appears.
A person without OCD may think:
What if I swerved into traffic?
and continue driving.
Someone with OCD may think:
Why did I have that thought?
What does it mean that I had it?
What if it means I secretly want to do it?
What if I can't trust myself?
How can I know for sure that I won't lose control?
And then the person may begin checking, analyzing, Googling, seeking reassurance, mentally reviewing what happened, monitoring their feelings, avoiding the situation, or performing some other compulsion.
The original intrusive thought has now become a problem to solve.
And the more the brain learns that certain thoughts require a response, the more important and threatening those thoughts can begin to feel.
This is a central part of the OCD cycle: thought → threat → compulsion → temporary relief → increased importance of the thought.
You can read more about this process in our article on The OCD Cycle.
Catching the “What-If” Train Leaving the Station
A helpful way to visualize what happens when an intrusive thought hits is the metaphor of the “What-If” Train.
Imagine sitting on a train platform. Every few minutes, a fast train labeled “What-If?” pulls into the station.
The train might say:
What if I swerved?
What if the door is unlocked?
What if this symptom means something serious?
What if I don't really love my partner?
What if that thought means something terrible about me?
The Everyday Mind
The train arrives, but you don't necessarily have to get on.
You notice the thought, perhaps feel a brief moment of discomfort, and let it roll right past.
The Anxious Mind
You might step onto the train briefly.
You look around. Is there actually something I need to deal with here?
If there is a practical problem, you address it. If there isn't, you step off at the next stop.
The OCD Mind
The train can feel impossible to ignore.
The second the engine pulls into the station, OCD convinces you that you must get aboard and ride it all the way to the end of the line.
One “What-If” leads directly into another:
What if the door is unlocked? → What if someone breaks in? → What if it's my fault? → What if I can't live with the guilt? → What if I need to check one more time?
Before you know it, you're miles away from where you actually started.
The goal of OCD treatment isn't to make sure the train never arrives.
It's learning that you don't have to get on every train that pulls into the station.
The Grammar of OCD: Absolutes vs. Flexible Thinking
What often forces you onto that train is the rigid, uncompromising language OCD uses in your head.
Ordinary anxiety thoughts—while uncomfortable—can still leave room for flexibility, preferences, and uncertainty.
OCD often shifts that language toward threat-based absolutes.
Everyday & Anxious MindsetOCD Intrusive Mindset“I want to make sure the door is locked.”“I must check the lock right now or something terrible could happen.”“I should double-check my email before hitting send.”“I have to ensure there are zero errors, or I won't be able to handle it.”“Maybe I misunderstood what they meant by that comment.”“I need absolute certainty about what they meant.”“It would be terrible if someone I love got sick.”“I cannot tolerate even the possibility of exposure.”“I'm worried about my health.”“I must verify this symptom immediately.”
Notice how words like want, should, maybe, and worried leave room for nuance.
In contrast, OCD often introduces rigid imperatives:
NEED. MUST. HAVE TO. CANNOT.
The problem isn't the words themselves. The problem is the felt requirement behind them: I cannot move forward until I know.
Four Characteristics of OCD Intrusive Thoughts
If you're trying to understand a troubling thought pattern, there are several characteristics that can help distinguish an OCD process from an ordinary intrusive thought.
1. A Refusal to Tolerate Ambiguity
OCD often demands absolute proof.
The thought tells you that living with an unanswered question is unacceptable and dangerous.
Did I lock it?
Do I really love them?
What if I accidentally hurt someone?
What if this symptom means something?
What if I made a mistake and don't remember?
Instead of allowing the question to remain unanswered, you feel compelled to solve it.
But OCD is very good at generating new questions.
2. Targeting What Matters Most
OCD often latches onto the things you care about most.
A devoted, gentle parent may experience thoughts of causing harm to their child.
A deeply honest professional may become consumed by the possibility that they accidentally committed fraud.
A highly compassionate person may experience thoughts about being secretly cruel or malicious.
Someone who values their health may become consumed by the possibility of having a serious illness.
The content varies.
But the common thread is often the same:
The thought matters enormously to you, and OCD uses that importance to make the thought feel even more threatening.
3. The “False Alarm” Sensation
An OCD intrusive thought can feel less like a quiet idea floating through your mind and more like a smoke detector going off in an empty room.
The thought may trigger an immediate surge of anxiety, disgust, guilt, dread, or urgency.
Your body is telling you:
PAY ATTENTION. THIS MATTERS. DO SOMETHING.
And because the feeling is so intense, it can be tempting to assume that the thought itself must be important.
But intensity is not evidence.
A thought can feel incredibly important without actually being important.
4. Thought-Action Fusion
OCD can also involve thought-action fusion—the tendency to treat having a thought as if it says something important about reality.
For example:
"Because I thought about something bad happening, maybe I increased the chances of it happening."
"If I had that thought, maybe it means I secretly wanted it."
"If I don't feel horrified enough by this thought, maybe that means something about me."
The thought becomes evidence.
But thoughts are not actions.
Having a thought is not the same thing as intending, wanting, or doing something.
And Not Every Compulsion Is Visible
One reason OCD can be difficult to recognize is that compulsions aren't always obvious.
You may not wash your hands or check the door twenty times.
Instead, your compulsions may happen almost entirely in your head.
You might:
Replay a conversation to determine exactly what you said
Analyze a thought to figure out what it “really means”
Check how you feel to determine whether you have the “right” feelings
Google symptoms or feared scenarios
Ask someone for reassurance
Mentally review memories
Compare possibilities over and over
Test yourself to see how you react
Try to prove to yourself that you're a good person
Reassure yourself that something won't happen
Avoid situations that trigger uncertainty
From the outside, this can look like ordinary thinking.
From the inside, it can feel like you cannot stop until you find the answer.
And that is an important distinction.
The question isn't simply:
“Am I thinking about this a lot?”
It may be more useful to ask:
“What am I trying to accomplish with this thinking?”
If you're repeatedly thinking in order to reach certainty, eliminate anxiety, prove that something is okay, or prevent a feared outcome, the thinking itself may be functioning as a compulsion.
Moving Forward at Red Elm
Experiencing intense intrusive thoughts does not mean you are flawed, dangerous, or weak.
Intrusive thoughts are a normal part of human cognition. The difficulty comes when a thought becomes so important, threatening, or uncertain that you feel compelled to analyze it, neutralize it, check it, avoid it, or seek reassurance about it.
At Red Elm Psychotherapy, we specialize in helping individuals navigate OCD and intrusive thoughts using compassionate, evidence-based approaches, including Exposure and Response Prevention (ERP).
Treatment isn't about proving that your feared outcome could never happen.
Instead, it is about learning that you can experience an intrusive thought, uncertainty, or discomfort without automatically doing what OCD tells you to do.
You can notice the thought.
You can notice the alarm.
You can let the What-If train arrive.
And you can choose not to get on.
The goal isn't to eliminate intrusive thoughts. It's to change your relationship with them so they no longer determine what you do next.
If intrusive thoughts are taking up significant time, driving compulsions or avoidance, or interfering with your ability to live your life, specialized OCD treatment may help.

Fertility, Early Pregnancy, and OCD: When Uncertainty Becomes Hard to Tolerate
Trying to conceive and early pregnancy can bring enormous uncertainty—and for someone with OCD, the search for reassurance and control can quickly take over. Learn how fertility and pregnancy OCD can turn uncertainty into checking, researching, and avoidance, and how ERP and ACT can help you make room for hope without needing a guarantee.
Maybe you’ve dreamed of being a mom since you were a little girl carrying around baby dolls and pretend bottles, or maybe motherhood is something you only knew you wanted later—but now it feels like something you can’t imagine your life without.
No matter when you decided you wanted to be a mom, from that moment on, the pressure can begin to build.
The things we want most are often the same things we feel like we need the most certainty about. And, as I’m always telling my patients, certainty doesn’t really exist—anywhere.
That can be incredibly difficult to accept when you are trying to get pregnant.
When you are running through checklists, taking ovulation tests, taking hormones, tracking cycles, taking temperatures, getting shots, going to acupuncture, changing your diet, taking supplements, and doing everything you possibly can to increase your chances of getting pregnant, it can feel exhausting that none of these activities guarantees that you are going to become a mother.
And even if you become pregnant, there is still no certainty.
Every appointment, scan, Doppler, and ultrasound can feel like another moment when you might find out that something has gone wrong.
For someone with fertility OCD or pregnancy OCD, this uncertainty can become particularly difficult to tolerate. OCD can turn an understandable desire for safety and certainty into an endless search for reassurance, information, and control.
We All Want Certainty When Something Matters This Much
The desire for certainty around pregnancy isn't irrational.
Pregnancy is a huge physical and emotional change. There are real medical risks. There are real decisions to make. There are things you can do to take care of yourself and your pregnancy.
And our culture often reinforces the idea that pregnancy should be approached with caution and vigilance.
Think about how commonly people are told to wait until 12 or 13 weeks to tell other people they're pregnant. There are good reasons someone might choose to wait—and deciding when to share a pregnancy is deeply personal. But it also reflects how uncomfortable we can be with allowing pregnancy to be both real and uncertain at the same time.
We often act as though there is some point at which you finally reach safety.
The first ultrasound.
The next blood test.
The heartbeat.
The end of the first trimester.
The anatomy scan.
The point at which the pregnancy is considered viable.
But there is no stage of pregnancy where safety is certain. And there isn't a stage of your child's life where safety becomes certain, either.
There will always be something that could happen that you cannot control.
That can be incredibly difficult to accept when the thing you want most is for your baby to be okay.
When Uncertainty Turns Into an OCD Cycle
When something matters enormously, our brains naturally look for ways to gain control.
During fertility treatment, that might mean carefully tracking everything, researching supplements, monitoring ovulation, changing your diet, analyzing symptoms, or trying to find the exact combination of things that will finally make pregnancy happen.
Some of these behaviors are completely reasonable. Fertility treatment involves real decisions, and there is nothing wrong with wanting to understand your options or follow your doctor's recommendations.
But sometimes the search for certainty starts to expand.
You may find yourself wanting another blood test, another ultrasound, another appointment, or another opinion—not because there is a specific medical reason for it, but because you are hoping the next piece of information will finally make you feel certain that everything is okay.
You may spend hours Googling symptoms, researching fertility outcomes, or looking for stories from other women who experienced the same thing.
And even when you get an answer, the relief may not last very long. Soon there is another question, another symptom, or another possibility to investigate.
This can be particularly difficult when you're actually undergoing fertility treatment. There can be legitimate reasons to ask your doctor more questions or to receive additional monitoring. But understanding the difference between gaining information and gaining reassurance can be important.
If you need information to make a reasonable medical decision, that's information.
If you need reassurance to make an uncomfortable feeling go away, that may be part of an OCD cycle.
The two can look very similar from the outside, but they serve very different purposes.
When Anxiety About Pregnancy Becomes the Problem
Fertility anxiety can become particularly cruel when you begin to worry that your anxiety is causing the problem.
You might think:
What if all this stress is making it harder for me to get pregnant?
What if I'm worrying too much?
What if my negative thoughts are affecting my body?
I know I need to relax, but I can't relax—and now I'm even more worried.
I've worked with patients who are frightened by something they ate or did and then become equally frightened by their reaction to it.
“I'm so worried that maybe eating a raw egg was a really bad and dangerous activity—but I know that my worry is even worse for me.”
Now there are two things to solve: the original uncertainty and your reaction to it.
This can create a particularly painful loop. You may start monitoring how anxious you are, trying to calm yourself down, judging yourself when you're stressed, or feeling like you need to achieve a certain emotional state before you can safely move forward.
But anxiety isn't a switch you can simply turn off.
And trying to eliminate anxiety can actually give it more power.
The Belief That You Have to Do Everything “Right”
I also see women become incredibly hard on themselves when pregnancy doesn't happen as quickly or easily as they hoped.
They may look around and think:
Other women get pregnant and don't do any of this.
I've done everything I'm supposed to do. Why don't I have a baby?
Maybe there is something really wrong with me.
This can turn fertility into a kind of moral test.
If I eat the right foods, take the right supplements, manage my stress, exercise the right amount, follow the treatment plan, think positively enough, and do everything correctly, maybe I can make this happen.
And if it doesn't happen, the conclusion can become:
I must have done something wrong.
But there is an enormous difference between taking reasonable steps to care for your fertility and believing that you can control the outcome if you just do everything perfectly.
You cannot control every outcome by doing everything correctly.
And that is one of the hardest truths about fertility—and one of the hardest truths for OCD to accept.
Why Early Pregnancy Can Make OCD Louder
For some people, getting a positive pregnancy test feels like the moment they have been waiting for.
And then the anxiety gets louder.
Suddenly there are physical sensations you've never experienced before.
Your body is changing.
You may be paying closer attention to every cramp, twinge, discharge, symptom, or lack of symptom.
There are foods to think about, medications to question, supplements to research, appointments to prepare for, and medical information coming at you from every direction.
Pregnancy is a huge health change, and that can give OCD a lot of material to work with.
If you've struggled with health OCD or anxiety about physical sensations before, pregnancy can make those fears much louder.
But even if OCD has never focused on your health or physical sensations before, pregnancy can create a completely new place for OCD to attach.
You might find yourself repeatedly asking:
Is this normal?
Could this mean something is wrong?
Did I do something that could hurt the baby?
Should I call my doctor?
Should I Google this?
Why do I feel different today than yesterday?
Again, some medical questions are completely appropriate. Pregnancy requires medical care and attention.
The question is what happens after you've gotten an answer.
Does the answer allow you to move on?
Or do you immediately need to ask another question, check another symptom, search another website, or get another reassurance?
When OCD Takes Away Your Ability to Hope
Not everyone responds to uncertainty by checking more.
Sometimes the response is to feel less.
You may avoid getting excited about the pregnancy.
You may hesitate to tell people.
You may avoid imagining the baby or making plans.
You may tell yourself not to get too attached.
You may feel like allowing yourself to feel happy is somehow tempting fate.
I've had patients say things like:
“I just can't attach to this baby because I am not sure if I'll really ever have this baby, but I feel guilty for not being willing to hold hope.”
This is another attempt to solve uncertainty.
If I don't let myself fully love this baby, maybe I won't be as devastated if something happens.
If I don't let myself believe this is really happening, maybe I'll be prepared.
But protecting yourself from possible pain also means protecting yourself from the experience that is happening right now.
And there is no way to know whether allowing yourself to hope will ultimately lead to joy or heartbreak.
That's the nature of loving something you cannot completely control.
Fertility and Pregnancy OCD Isn't About Caring Too Much
This is an important distinction.
The goal of treatment isn't to convince you that fertility doesn't matter.
It isn't to make you stop caring about your pregnancy.
It isn't to make you become someone who doesn't worry about medical decisions or potential risks.
And it certainly isn't to convince you that everything will be okay.
The goal is to help you develop a different relationship with uncertainty.
How ERP and ACT Can Help With Fertility and Pregnancy OCD
In therapy, we may work on accepting the things you cannot know.
You may not know whether this fertility treatment will work.
You may not know when you will become pregnant.
You may not know whether every symptom you experience during pregnancy is completely benign.
You may not know exactly how your pregnancy will unfold.
And you may not be able to make yourself certain by thinking about it harder.
For someone with OCD, Exposure and Response Prevention (ERP) can help you practice experiencing uncertainty without responding with the compulsions that temporarily make you feel safer.
Acceptance and Commitment Therapy (ACT) can help you notice the thoughts and feelings that show up without allowing them to dictate your behavior.
Together, these approaches can help you ask a different question.
Instead of:
“How can I make sure everything will be okay?”
You begin asking:
“How do I want to live while I don't know?”
That might mean allowing yourself to be excited.
It might mean telling someone you are pregnant.
It might mean noticing a physical sensation without immediately researching it.
It might mean following reasonable medical guidance without trying to eliminate every possible risk.
It might mean letting yourself love this baby even though you cannot guarantee that you will get to bring this baby home.
And it might mean allowing yourself to experience disappointment, fear, grief, or uncertainty without treating those feelings as problems you have to solve.
When Fertility or Pregnancy Anxiety May Be More Than Anxiety
You don't have to wait until anxiety is completely debilitating to seek help.
It may be time to consider specialized support if you find yourself:
spending hours researching fertility, pregnancy, symptoms, or potential risks
repeatedly seeking reassurance from your partner, doctors, friends, or online communities
requesting repeated testing or monitoring primarily to feel reassured
constantly monitoring physical sensations
avoiding foods, activities, people, or experiences because of fear
feeling unable to allow yourself to feel excited about a pregnancy
trying to prevent yourself from becoming attached to your baby
spending significant amounts of time trying to determine whether you're “doing pregnancy right”
finding that reassurance helps temporarily, but you quickly need it again
having anxiety that interferes with your relationships, work, sleep, or ability to be present in your life
These experiences don't mean that you don't want your pregnancy enough, that you're doing something wrong, or that you're failing to be grateful.
They may mean that anxiety or OCD has begun asking you to do something that isn't actually possible: make an uncertain situation certain.
You Don't Have to Know How This Ends to Be Here Now
You can desperately want to become a mother and still not know when or whether it will happen.
You can be afraid and still allow yourself to hope.
You can take reasonable care of yourself without believing that you have to do everything perfectly.
You can be pregnant and know that pregnancy carries risks without spending every moment trying to eliminate those risks.
And you can love something deeply even when you cannot guarantee that you will get to keep it.
You don't have to eliminate uncertainty before you are allowed to live according to your values.
Sometimes the work is learning that you can carry the uncertainty—and still make room for hope, love, attachment, and the parts of motherhood that are already happening.
Fertility and Pregnancy OCD Therapy
You don't have to wait until anxiety is completely overwhelming to get help. At Red Elm Psychotherapy, we specialize in OCD and perinatal mental health, using evidence-based approaches including Exposure and Response Prevention (ERP) and Acceptance and Commitment Therapy (ACT) to help women navigate fertility, pregnancy, and the uncertainty that comes with both.

Postpartum OCD vs. Postpartum Psychosis: What Mothers Need to Know
When a frightening news story about postpartum psychosis makes you wonder, “What if that happens to me?” it can be especially terrifying if you already experience postpartum OCD. Learn how intrusive thoughts, OCD, and postpartum psychosis differ—and when it’s time to seek help.
If you’re a new mother, or you work with new mothers, you’ve probably heard of the Lindsey Clancy case. It feels like every time I pick up my phone, open my computer, sit down with a client, or run into a friend, someone is talking about the case.
Given my work with women in the perinatal period, and particularly with intrusive thoughts and OCD, this isn’t entirely unexpected. But beneath the curiosity, I’ve noticed something else coming up again and again: fear.
So many women are afraid this could be them. This is particularly true for women struggling with intrusive thoughts about harming their child. This case can feel like their worst nightmares coming true.
When Postpartum OCD Makes You Afraid of Your Own Mind
Women with postpartum OCD and intrusive thoughts about harming their baby often come to me in a state of emergency. They may fear that the thoughts they are having are dangerous. Sometimes it’s the first time a woman has ever had thoughts like this, so she is often afraid it means she is “going crazy” or could really hurt her baby.
She may feel exhausted, changed dramatically by motherhood, or traumatized by a difficult birth or complications during pregnancy or after birth. These changes, combined with terrifying intrusive thoughts, can make women feel like they are “losing control.”
Postpartum OCD can involve frightening, unwanted intrusive thoughts, images, or urges—sometimes involving harm coming to the baby. These thoughts can feel incredibly meaningful to the person experiencing them, particularly when OCD convinces her that having a thought says something about who she is or what she might do.
The more frightening the thought feels, the more urgently she may try to figure it out. She might check her feelings, ask for reassurance, avoid certain situations, repeatedly search the internet, or monitor herself for signs that she is becoming dangerous.
But Postpartum OCD and Postpartum Psychosis Are Different
Postpartum psychosis is a different clinical experience. It can involve hallucinations, delusions, severe confusion, disorganized behavior, paranoia, and significant changes in a person's perception of reality or functioning. It is a psychiatric emergency and requires immediate evaluation.
With OCD, the intrusive thoughts are typically unwanted and distressing. The person is often afraid of what the thought might mean and may begin monitoring, checking, avoiding, or seeking reassurance to make sure the feared thing won't happen.
Despite these differences, women with postpartum OCD are often afraid of becoming psychotic, losing control, or hurting their children. It can feel like a “good mom” should be able to guarantee that her children are safe—or, at the very least, guarantee that her children are safe from her.
When cases like this come up, that fear can become an obsession of its own. A woman who is already afraid of losing control may begin monitoring herself for any sign that she is becoming psychotic or dangerous. She may spend hours researching symptoms, analyzing her thoughts, or asking herself whether she can trust her own mind.
We Don't Get Perfect Certainty
The truth is, we cannot guarantee our children’s safety from everything. We can seek help, find support, and be honest about what we're experiencing. We can learn what to look for when something changes and know when more care is needed.
But safety is not certain.
When I’m working with a mom experiencing OCD, this reality can feel crushing. And when we see a brutal reality like this in the news, that uncertainty can feel even harder to tolerate.
OCD asks us to take the possibility of losing control very seriously. It can make a thought feel like a warning and a fear feel like a prediction. But a frightening thought is not the same thing as an intention, and fear of losing control is not the same thing as actually losing control.
Having intrusive harm thoughts in the context of OCD does not, by itself, mean that someone is at increased risk of acting on them. At the same time, significant changes in perception, thinking, behavior, or functioning can signal that something more serious is happening and warrant prompt psychiatric evaluation.
Part of my job is helping women understand what they’re experiencing, recognize when OCD is driving them to seek certainty, and figure out when additional care or support may be needed.
Safety is never guaranteed. But neither is this something you have to figure out or carry alone.
What We Can Do Better
We can do a better job educating mothers, partners, families, and healthcare providers about postpartum mental health.
Mothers should know that frightening intrusive thoughts do not automatically mean they are dangerous or losing touch with reality. They should also know that significant changes in perception, thinking, behavior, or functioning can be signs that something more serious is happening and deserve prompt psychiatric evaluation.
We don't need mothers to diagnose themselves. We need them to know that they can ask for help—and we need a system that is actually able to help them.
Getting Help
If your thoughts have started to scare you, or you find yourself spending hours researching this case—or other cases like it—you don't have to figure this out alone.
I'd love to connect. I know how terrifying this time can be. You don't need to spend hours trying to determine what your thoughts mean or whether you're safe. We can slow it down, make sense of what's happening, and figure out what you need from here.
If you're experiencing postpartum intrusive thoughts or are worried about postpartum OCD, Red Elm Psychotherapy offers specialized OCD and perinatal mental health therapy.
If you or someone you love is experiencing hallucinations, delusions, severe confusion, or a significant loss of contact with reality after childbirth, seek immediate psychiatric or emergency medical care.
For additional support and guidance around perinatal mental health, contact Postpartum Support International (PSI) at 1-800-944-4773 or visit Postpartum Support International.

When Reality Feels Unstable: Understanding Existential OCD
When Curiosity Turns into a Search for Certainty
Deep thinkers often pride themselves on asking big questions. But when Existential OCD takes hold, fascinating inquiries about reality, consciousness, and purpose transform into urgent, terrifying emergencies.
Healing doesn’t mean giving up your curiosity or shutting down your analytical mind—it means building deep roots in the present moment so you can carry life’s unanswerable questions without letting them pull you away from living.
Alex had always been a deep thinker.
Growing up, he was the friend who stayed up past midnight discussing the scale of the universe, the mysteries of consciousness, and the search for meaning. He loved learning, reading, and exploring ideas most people took for granted. His curiosity wasn't just a trait—it was his superpower, and part of what made him so successful.
But over time, something subtle and terrifying shifted.
A thought that once felt like a fascinating mental exercise suddenly felt like a threat:
“How do I actually know any of this is real?”
At first, Alex brushed it off. Everyone has weird, fleeting thoughts. But then the question returned—and this time, it wouldn’t leave.
It intruded while he was sitting at his desk at work. While he was driving home on the highway. While he was looking into the eyes of someone he loved.
Soon, Alex’s mind was flooded with a continuous stream of unanswerable questions:
“What if I’m the only conscious person alive?”
“What if everyone else is just a projection of my mind?”
“What if life is a simulation?”
“What if there is no objective meaning to anything?”
“What if I’m trapped like this forever and never feel 'normal' again?”
These didn't feel like interesting philosophical debates anymore. They felt like emergencies. They felt like catastrophic errors in reality that he was required to solve immediately.
When Curiosity Turns Into a Search for Certainty
Alex did what any analytical person would do when faced with a crisis: he tried to think his way out of it.
He devoured neuroscientific studies and articles on consciousness.
He watched hours of debates between theoretical physicists and philosophers.
He searched online forums late into the night, looking for anyone who felt the same way.
Occasionally, he’d find a sentence or an argument that brought a rush of relief. For a few minutes, his body would relax.
Then the counter-argument hit:“Yes, but how can anyone really know for sure?”
And just like that, he was back at square one.
The more he tried to force certainty, the more urgent the need for certainty became. Eventually, Alex noticed a painful reality: He was spending less time living his life and more time trying to prove that his life was real.
He could sit at dinner with close friends, physically present, but internally miles away, wrestling with a mental proof of existence. He could achieve a major milestone at work, only to instantly mute the joy with: "Does any of this actually matter?"
Underneath the endless mental gymnastics was a single, terrifying core fear: “What if I never get out of this mental prison?”
The Hidden Cycle of Existential OCD
Many people with existential OCD do not realize they are experiencing OCD because the compulsions are often invisible.
There may not be outward rituals or behaviors that other people notice.
Instead, the compulsions often happen internally.
They can include:
Analyzing questions about existence for hours
Researching philosophy, science, or spirituality for reassurance
Mentally debating different possibilities
Trying to prove that reality is real
Checking whether things or people feel “real”
Asking others for reassurance
Reviewing memories or experiences to find certainty
Avoiding situations that trigger existential thoughts
The questions themselves are not the problem.
Humans have wondered about consciousness, mortality, meaning, and existence for thousands of years.
The painful part is the feeling that you cannot move forward until you have an answer.
Why Existential OCD Feels So Convincing
Existential OCD can be especially difficult because the questions are genuinely meaningful.
These are not random fears.
They touch on some of the biggest questions humans have ever asked.
That is part of why the thoughts can feel so powerful.
Your brain may tell you:
“This is important. You cannot ignore this.”
“You need to figure this out before you can relax.”
“If you stop thinking about this, you might miss something.”
For someone who is naturally curious and thoughtful, this can become an exhausting trap.
The very skills that help you learn, solve problems, and understand the world can become pulled into an endless search for certainty.
The goal of treatment is not to make you less thoughtful.
It is to help you recognize when thinking is helping you—and when OCD has turned thinking into a compulsion.
Learning to Live With Uncertainty
When Alex began therapy, he wanted certainty.
He wanted someone to explain why these thoughts were happening.
He wanted reassurance that he was okay.
He wanted to know that reality was real.
And it made sense that he wanted those things.
When your brain sends the message “You need to solve this,” it can feel almost impossible not to listen.
But recovery from existential OCD does not come from finding the perfect answer.
It comes from learning that you can have the question without needing to solve it.
Over time, Alex practiced responding differently.
When the thought appeared:
“What if none of this is real?”
He practiced noticing the thought without entering into hours of analysis.
He practiced feeling the urge to research without immediately searching for answers.
He practiced allowing uncertainty to be present while returning attention to what mattered in his life.
Not because he had finally proven the thought wrong.
But because he learned something more important:
He could handle not knowing.
What Therapy for Existential OCD Feels Like at Red Elm
Many people who come to Red Elm Psychotherapy for existential OCD have spent months—or years—trying to think their way out of their fears.
They may have searched for explanations.
They may have read countless articles.
They may have asked loved ones for reassurance.
They may have hoped that finding the right answer would finally bring peace.
And we understand why.
When something feels deeply unsettling, wanting certainty is a very human response.
At Red Elm, we do not dismiss these questions.
Questions about reality, consciousness, death, and meaning are some of the most profound questions people can ask.
But we also understand how OCD can turn these questions into a cycle of fear, rumination, and endless searching.
Our work is not about convincing you of a particular answer.
It is not about telling you to stop thinking.
It is about helping you build a different relationship with uncertainty.
You can have an unanswered question and still be okay.
You can feel anxiety without treating it like an emergency.
You can experience doubt without letting it take over your life.
You Do Not Have to Solve Existence Before You Can Start Living
One of the most painful parts of existential OCD is the fear that you will always feel this way.
Many people wonder:
“What if I am stuck like this forever?”
“What if I never feel present again?”
“What if I can never enjoy life the way I used to?”
But existential OCD is treatable.
Healing does not mean you will never wonder about life’s biggest questions again.
It means those questions no longer control your day.
You can be curious without being trapped.
You can be thoughtful without getting lost.
You can wonder about existence while still being present for your own.
At Red Elm Psychotherapy, we specialize in OCD treatment using Exposure and Response Prevention (ERP) to help people step out of cycles of rumination, reassurance-seeking, and uncertainty.
If you recognize yourself in Alex’s story, you are not alone.
There is a way forward.
The Invisible Cycle of Existential OCD
Many people suffering from Existential OCD (eOCD) have no idea they have OCD at all.
When most people think of OCD, they picture visible rituals like hand-washing, door-checking, or lining objects up. But in existential OCD, the compulsions are almost entirely invisible. They happen silently inside the mind.
Common Mental Compulsions in Existential OCD:
Hyper-analyzing: Ruminating on existential or philosophical questions for hours.
Compulsive Researching: Binge-reading philosophy, physics, or spiritual texts for reassurance.
Reality-Checking: Constantly monitoring your perception to check if things or people feel "real" or "connected."
Memory Reviewing: Scrutinizing past memories to prove to yourself that your mind is functioning correctly.
Reassurance-Seeking: Asking loved ones, "Do you ever feel like nothing is real?" just to feel grounded.
Avoidance: Steering clear of triggers like space documentaries, philosophy classes, high ceilings, or quiet rooms.
The Core Rule of eOCD: The questions themselves aren't the problem. Humans have pondered consciousness, death, and meaning for millennia. The problem is the OCD brain telling you that you cannot live, relax, or be safe until you have a 100% guaranteed answer.
Why Existential OCD is So Convincing
Existential OCD is a uniquely deceptive form of OCD because the themes are genuinely profound.
These aren't irrational, random fears like checking if the stove is on five times. They touch on the deepest, most complex mysteries of human existence. Because the topics are important, your brain tricks you into believing the alarm bells are justified:
"This is too important to ignore."
"You can't go back to normal life until you figure this out."
"If you stop thinking about this, you're just living in denial."
For a naturally curious, intelligent person, this is the ultimate trap. The exact cognitive strengths you use to succeed—problem-solving, critical thinking, deep focus—are hijacked by OCD into an endless, exhausting loop.
The goal of treatment isn't to make you stop being a deep thinker. It's to untangle your intelligence from OCD's demand for absolute certainty.
Learning to Live With the Unanswerable
When Alex first walked into therapy, he wasn't looking for a strategy—he was looking for answers. He wanted a guarantee that he was okay, that his thoughts were just a phase, and that reality was definitively real.
It made complete sense. When your nervous system is screaming that you're in danger, wanting certainty is human nature.
But true recovery from Existential OCD doesn't come from finding the ultimate answer to life’s mysteries. It comes from learning that you can carry an unanswered question without letting it stop your life.
With guidance, Alex began to change his relationship with his thoughts:
When the thought spiked—“What if none of this is real?”—he practiced acknowledging the thought without launching a three-hour mental investigation.
When the urge to spend hours on Reddit or philosophical forums hit, he practiced sitting with the discomfort without acting on it.
He allowed the feeling of uncertainty to exist in the background while shifting his attention back to what actually mattered: his relationships, his passions, and his present moment.
He didn't recover because he solved the puzzle of existence. He recovered because he proved to himself that he could handle not knowing.
Healing at Red Elm Psychotherapy
If you’ve spent months or years trying to think, research, or analyze your way out of existential dread, we want you to know something vital: You are not crazy, and you are not broken.
At Red Elm Psychotherapy, we don't dismiss your questions. Thoughts about consciousness, death, reality, and purpose are some of the most human experiences we can have. But we also recognize when OCD has weaponized those questions against you, turning deep thinking into an endless cycle of panic and rumination.
Our approach isn't about giving you philosophical answers or telling you to "just stop thinking."
Using evidence-based treatments like Exposure and Response Prevention (ERP) we help you:
Break the cycle of mental compulsions and endless research.
Disarm the urgency behind existential alarm bells.
Build a peaceful, resilient relationship with uncertainty.
Re-engage with the richness of your daily life—right here, right now.
You don't have to solve the mysteries of the universe before you’re allowed to start living again.
Ready to Step Out of the Loop?
If Alex’s story feels all too familiar, you don't have to navigate this alone. Contact Red Elm Psychotherapy today to schedule a consultation and take the first step toward getting your life back from OCD.
Note on Confidentiality: The story of "Alex" is a composite narrative created for illustrative and educational purposes only. It does not represent any single individual or client at Red Elm Psychotherapy. Any resemblance to real persons or events is entirely coincidental.

When Being a "Good Mom" Feels Like a Prison: The Hidden Face of Postpartum OCD
You love your baby more than anything—but what if your desire to protect them has started stealing your peace? Postpartum OCD often hides behind “good motherhood,” convincing moms that one more precaution, one more check, or one more reassurance will finally create safety. Learn why OCD is really a struggle with uncertainty—and how ERP therapy helps moms reclaim their confidence.
By Dr. Erin Cook, PsyD, PMH-C | Red Elm Psychotherapy
It's 3:00 AM and your baby is finally asleep. Instead of resting, you're awake on Amazon comparing medical-grade sanitizing wipes for stroller wheels. You've already washed the pacifier four times tonight, your hands sting from the harsh soap, and your mind keeps whispering: “Just a few more steps and my baby will be safe.”
The next day, you tentatively mention your exhaustion to another mom. She smiles sympathetically and says, "Honestly, you can never be too careful these days. You're just such a good mom."
And suddenly, instead of recognizing how miserable you are, society accidentally reinforces the very clinical anxiety that is keeping you trapped.
How Anxiety Hides Behind "Good" Motherhood
One of the hardest parts about postpartum OCD (Obsessive-Compulsive Disorder) is that it constantly hides behind behaviors our culture celebrates. We praise mothers for sacrificing their sleep, admire moms who are endlessly vigilant, and celebrate the parent who has researched every chemical, anticipated every danger, and stayed one step ahead of every possible threat.
Our culture has created a difficult equation: we often celebrate constant hypervigilance as the mark of a devoted mother. It's easy to start believing that if you could just be careful enough, you could prevent every bad outcome.
Because of this cultural camouflage, it can be incredibly difficult to recognize when a healthy protective instinct has crossed the line into a clinical issue.
Imagine an adult without children washing every doorknob in their home fifty times a day because they're terrified of contamination. Most people would immediately recognize that as a sign of OCD. Now imagine a brand-new mother disinfecting every bottle, throwing away food because it might have touched a "dirty" counter, or spending hours tracking ambient air quality.
People call her responsible. Careful. Protective. Meanwhile, she is quietly unraveling inside.
The Trap of Postpartum Contamination OCD: Moving the Goalposts
Postpartum OCD has an exhausting way of convincing you that just one more precaution will finally grant you peace of mind. It tells you safety is just around the corner if you do:
One more Google search about infant illness.
One more boiling sterilization cycle for the pump parts.
One more frantic portal message to your pediatrician.
One more reassurance-seeking question to your partner.
But the relief never lasts. Within minutes, your brain finds another terrifying possibility, another looming uncertainty, or another microscopic threat you should have anticipated.
That is because OCD doesn't actually care about safety—it demands absolute certainty. And absolute certainty does not exist when you are raising a living, breathing human being in an unpredictable world.
Why Perinatal OCD Hijacks Your Best Instincts
"I just want to be a good mom and keep my baby safe."
In our Vienna, VA psychotherapy practice, this is the exact sentence Niles and I hear most often from suffering mothers. They don't want perfect floors or pristine houses; they want to protect their child.
That is what makes perinatal OCD so heartbreaking. It hijacks the most beautiful, fierce, instinctive part of being a parent—your desire to protect your baby—and slowly turns it into a psychological prison. Underneath your exhausting rituals isn't irrationality; there is profound love.
But OCD quietly adds one devastating, false assumption to that love: If something bad ever happens, it means you didn't do enough.
Good Parenting is Not Risk Elimination
Every parent makes hundreds of choices a day that involve inherent risk. We buckle our children into car seats—not because they make driving 100% safe, but because they make it safer. We hold their hand crossing a parking lot, knowing we still can't control every distracted driver.
Good parenting has never been about achieving zero risk. It is about making thoughtful decisions while accepting that some uncertainty remains.
There is no magical checklist that guarantees a child will never get sick. No amount of obsessive cleaning eliminates every environmental risk. OCD treats this natural human uncertainty like an emergency that must be solved right now, promising you that if you just wash longer or research harder, you'll finally earn the peace you long for.
The goalpost will always move.
Because the goal of motherhood isn't becoming certain.
The goal of motherhood is learning to love deeply in a world where certainty doesn't exist.
You were never meant to carry the impossible responsibility of guaranteeing your child's safety. No parent can.
What ERP Therapy Actually Looks Like at Red Elm Psychotherapy
Many moms avoid reaching out for help because they are terrified of what treatment entails. They worry a therapist is going to force them to stop caring about germs altogether, or command them to be "gross" or reckless with their baby.
As specialized ERP clinicians, we want you to know: That is not what treatment looks like.
Exposure and Response Prevention (ERP), the gold-standard evidence-based treatment for OCD, isn't about becoming careless. It doesn't ask you to ignore legitimate pediatric health recommendations. Instead, it helps you build the skills to notice when anxiety—not your actual parenting values—is calling the shots.
Healthy caution asks:
"Have I taken reasonable, common-sense steps to care for my baby?"Postpartum OCD asks:
"But how can I be 100% absolutely sure there isn't a single germ left?"
ERP helps you learn to recognize the difference.
ERP helps you tell the difference. Recovery isn't about caring less about your child. It's about no longer confusing certainty with love.

Putting Down the Shield
Think of your postpartum anxiety like carrying a massive, heavy iron shield. At first, it made perfect sense to pick it up. Of course you want to protect your newborn.
But over time, OCD convinces you that you can never set that shield down. You sleep with it. You eat with it. You end up holding your baby awkwardly with one arm because your other arm is always white-knuckled, gripping the heavy shield. Eventually, the very tool meant to protect your family becomes the weight that keeps you from fully living.
ERP therapy doesn't ask you to abandon your child's safety. It simply helps you put the shield down when anxiety—not actual danger—is demanding you carry it. Because when your hands aren't occupied by fear, they are finally free to hold your baby, to rest, and to notice the beautiful moments that OCD has been stealing from you.
Postpartum OCD Therapy in Vienna, Virginia & Across PSYPACT States
If your "good mom" habits have started to feel like a prison, you do not have to keep carrying this weight alone.
At Red Elm Psychotherapy, we specialize in helping mothers recover from the exhausting cycles of postpartum OCD and perinatal anxiety using evidence-based, compassionate ERP. We provide specialized, non-judgmental care tailored to the unique pressures of motherhood.
We offer in-person therapy sessions at our office in Vienna, Virginia, as well as convenient virtual teletherapy across Virginia and multiple states via PSYPACT.
Recovery isn't about becoming a less careful mother—it’s about becoming a free one. Let's work together to help you put down the shield and start enjoying your baby again.

Face Your Fears, Change Your Brain: What to Expect in ERP Therapy for OCD
ERP therapy can sound scary: “Wait…you want me to face the thing I’m most afraid of?”
But ERP isn’t about forcing yourself to be fearless. It’s about learning that anxiety, uncertainty, and intrusive thoughts don’t have to control your life.
In our newest blog, we walk through what ERP therapy actually looks like—from understanding your OCD cycle to practicing new ways of responding.
If you’re struggling with OCD, intrusive thoughts, or perinatal OCD, you’re not alone.
If you’re searching for ERP therapy for OCD in Virginia, you may already know what it feels like to be stuck in the OCD cycle.
A thought shows up.
Your anxiety spikes.
Your brain tells you that you need to figure it out, prevent something bad from happening, or get reassurance before you can move on.
Maybe you find yourself:
Asking others for reassurance again and again
Avoiding situations that feel unsafe
Mentally reviewing conversations, memories, or decisions
Trying to “cancel out” intrusive thoughts
Checking until something finally feels right
These strategies make sense. They are your brain’s attempt to protect you.
The problem is that OCD learns from what you do next. Every time you respond to anxiety with a compulsion, your brain gets the message:
"This thought must have been important. I needed to do something to feel safe."
Over time, the cycle becomes stronger.
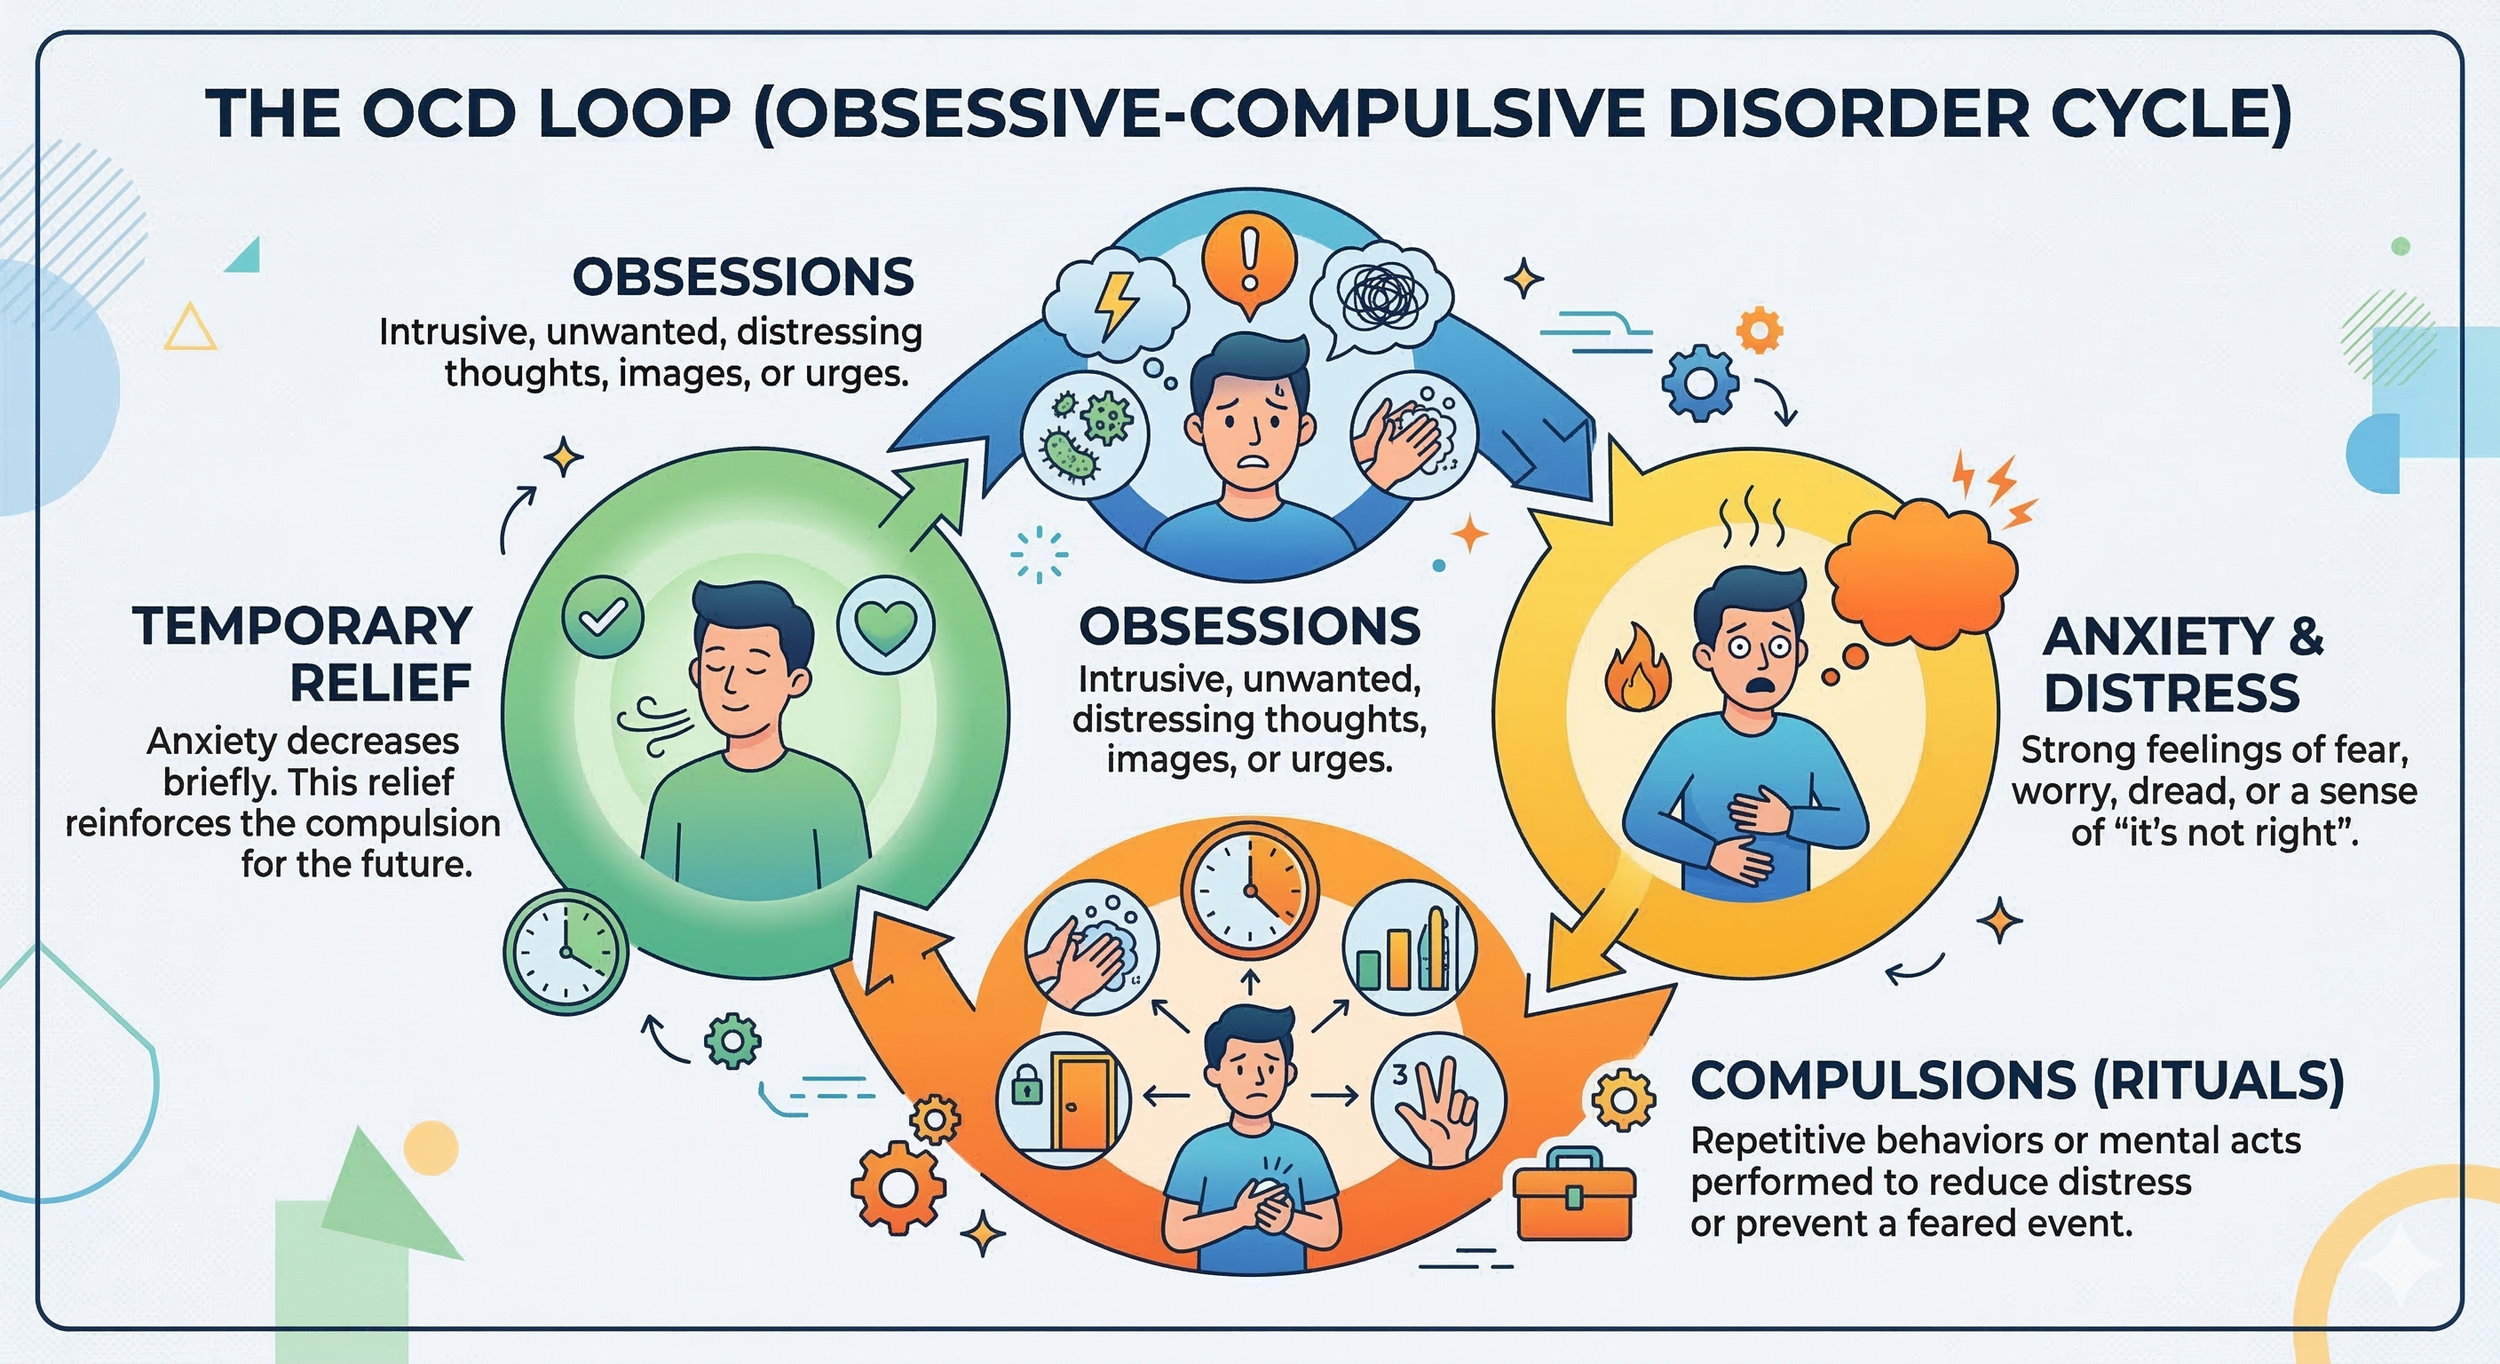
Exposure and Response Prevention (ERP) therapy helps your brain learn a different message:
"I can experience uncertainty. I can feel anxiety. I can have an intrusive thought—and I do not have to respond to it."
At Red Elm Psychotherapy, we specialize in ERP therapy for OCD, intrusive thoughts, and perinatal OCD, serving clients across Virginia and through PSYPACT telehealth.
What Is ERP Therapy for OCD?
Exposure and Response Prevention (ERP) is a specialized form of cognitive behavioral therapy designed specifically to treat OCD.
The name can sound intimidating. Many people hear “exposure” and imagine being forced to face their biggest fear immediately.
That is not what good ERP looks like.
ERP is a collaborative process where you and your therapist identify the patterns that keep OCD going and gradually practice responding differently.
The goal is not to eliminate anxiety forever.
The goal is to stop letting anxiety and OCD make your decisions for you.
ERP involves two parts:
Exposure: Gently and intentionally approaching thoughts, situations, sensations, or uncertainties that OCD tells you to avoid.
Response Prevention: Practicing not engaging in compulsions that temporarily reduce anxiety but keep OCD stuck over time.
What Happens in ERP Therapy?
Understanding Your OCD Cycle
Before starting ERP, your therapist will help you understand how OCD is keeping you stuck.
Together, you’ll look at the thoughts or fears that trigger anxiety and the things you do afterward to try to feel safe or certain.
For many people, those responses are not obvious. They may look like checking, asking for reassurance, avoiding situations, or spending hours trying to analyze a thought until it finally feels resolved.
The problem is that OCD keeps moving the finish line. No amount of checking, analyzing, or reassurance can create the complete certainty OCD is demanding.
ERP helps you begin stepping out of that cycle.Creating a Personalized Exposure Plan
ERP does not mean walking into your biggest fear on the first day of therapy.
Instead, you and your therapist create a gradual plan for practicing uncertainty. This might include approaching situations you have been avoiding, allowing uncomfortable thoughts to be present, or practicing not engaging in the rituals that OCD demands.
The objective is to help you discover that you can experience discomfort and still safely move forward
Learning to Respond Differently
This is the heart of ERP.
When OCD shows up, it often creates a sense of urgency:
"You need to figure this out right now."
"You need to make sure."
"You cannot move on until you feel certain."
ERP helps you practice a different response.
Instead of:
"How do I make this anxiety go away?"
you learn:
"Can I allow this feeling to be here while continuing with my life?"
This might mean resisting the urge to check, avoiding reassurance seeking, or allowing an intrusive thought to exist without trying to analyze what it means.
Over time, your brain learns that anxiety is uncomfortable—but it is not an emergency.
What Changes With ERP?
Over time, many people notice that OCD begins to take up less space.
You may find yourself:
Spending less time analyzing and seeking reassurance
Feeling less controlled by intrusive thoughts
Making decisions based on your values instead of fear
Anxiety and fear can come up, but they no longer make the rules.
ERP Therapy for Perinatal OCD: When Intrusive Thoughts Feel Terrifying
Perinatal OCD can show up as frightening intrusive thoughts, intense guilt, repeated reassurance seeking, or avoiding situations that feel risky. Many mothers find themselves caught in a cycle of trying to prove they are safe, responsible, and "good enough"-but the search for certainty never quite ends.
A Perinatal OCD Example
Many mothers with perinatal OCD describe an experience like this:
After the birth of her baby, a mother begins experiencing intrusive thoughts about something terrible happening. The thoughts feel vivid, unwanted, and deeply upsetting.
She starts wondering:
"What if this thought means something? What if I can't trust myself?"
She begins avoiding situations that trigger anxiety, asking her partner for reassurance, and mentally reviewing moments to figure out whether she missed something.
What makes ERP feel so difficult is not just the anxiety.
It is the feeling that not responding to the thoughts would be irresponsible.
"If there is even a small chance something could happen, shouldn't I do everything I can to prevent it?"
This fear is one reason perinatal OCD can feel so convincing.
Mothers are often surrounded by messages that they should anticipate every possible danger, prevent every mistake, and always know the right thing to do. OCD can take that understandable desire to protect and turn it into an impossible demand for certainty.
In ERP, the goal is not to prove that nothing bad could ever happen.
Instead, therapy focuses on learning that intrusive thoughts are not warnings or commands.
For example, an exposure might involve allowing an intrusive thought to be present during a normal parenting activity while practicing not engaging in compulsions that keep OCD going—such as reassurance seeking, mental reviewing, or avoidance.
The goal is not to become careless.
The goal is to learn that you can be a caring, responsible mother without needing absolute certainty before you trust yourself.
Over time, many mothers find that the thoughts become less urgent, and they are able to spend more time being present with their babies instead of constantly trying to prevent imagined dangers.
This is a fictional example created to illustrate how perinatal OCD can show up and how ERP therapy works.
ERP Therapy in Virginia and Through PSYPACT Telehealth
Finding specialized OCD treatment can be challenging. Many therapists are trained in general anxiety treatment but do not have specific training in ERP.
At Red Elm Psychotherapy, we provide:
OCD therapy in Vienna, VA
ERP therapy for OCD in Northern Virginia
Virtual ERP therapy across participating PSYPACT states
Specialized treatment for perinatal OCD and intrusive thoughts
You do not have to spend years trying to outthink OCD.
Start ERP Therapy for OCD in Virginia
If you are struggling with OCD, intrusive thoughts, or perinatal OCD, therapy can help you break free from the cycle of fear and compulsions.
Starting ERP can feel intimidating—but you do not have to feel completely ready before reaching out.
Many people begin therapy feeling unsure, scared, or convinced their thoughts are different from everyone else’s.
You are not the first person to bring these fears into therapy.
At Red Elm Psychotherapy, we provide compassionate, specialized ERP therapy for OCD across Virginia and through PSYPACT telehealth.
Schedule a consultation to learn how ERP therapy can help you move toward a life that is guided by your values—not by OCD.

How to Find an OCD Specialist in Northern Virginia (And Why Specialization Matters)
Not all therapy approaches treat OCD effectively. Learn why Exposure and Response Prevention (ER) is considered the gold- standard treatment, how to find an OCD specialist in Northern Virginia, and what questions to ask when choosing a therapost. We also discuss why specialized care is especially important during pregnancy and postpartum.
If you’ve been in therapy before and still feel like OCD is running your life, you’re not alone.
Many people with OCD spend months—or even years—in therapy before receiving treatment that actually targets OCD. They may leave sessions feeling understood and supported, yet still find themselves trapped in the same exhausting cycle of intrusive thoughts, compulsions, reassurance-seeking, and self-doubt.
That doesn’t mean therapy can’t help.
It usually means you haven’t been given the right treatment for OCD.
At Red Elm Psychotherapy, we specialize in treating OCD using Exposure and Response Prevention (ERP), the gold-standard treatment for OCD. We often meet clients across Northern Virginia who tell us, “I’ve been in therapy for years, but no one ever explained OCD this way.”
Why General Therapy Isn’t Always Enough for OCD
Standard therapy tools are incredibly valuable.
Supportive therapy can help people navigate grief, relationship challenges, work stress, trauma, depression, and major life transitions. Many compassionate therapists provide exceptional care using these approaches.
But OCD works differently.
Imagine breaking your arm. Your primary care physician is highly trained and incredibly knowledgeable—but they’re still likely to refer you to an orthopedic surgeon. Not because your primary care doctor isn’t good at their job, but because certain conditions require specialized expertise.
OCD is much the same.
OCD is driven by a cycle of intrusive thoughts, anxiety, compulsions, and temporary relief. Because of how this cycle works, some therapy strategies that are helpful for other concerns can unintentionally strengthen OCD.
For example, spending time analyzing why you had a particular thought, searching for certainty, or repeatedly offering reassurance can actually reinforce OCD’s message that the thought is dangerous and must be solved.
It’s not that those therapy approaches are “wrong.”
It’s that OCD requires a different blueprint.
Why Exposure and Response Prevention (ERP) Works
ERP is considered the gold-standard treatment for OCD because it targets the cycle that keeps OCD alive.
Rather than trying to convince you that your intrusive thoughts aren’t true, ERP teaches your brain something much more powerful:
You can experience uncertainty, anxiety, or intrusive thoughts—and choose not to respond with compulsions.
That might mean resisting mental checking, avoiding reassurance, postponing Google searches, stopping confession rituals, or gradually approaching situations OCD has taught you to fear.
Over time, your brain begins to learn that anxiety naturally rises and falls without needing compulsions to make it disappear.
This process helps retrain your brain’s alarm system. Instead of learning, “I survived because I checked,” your brain begins learning, “I survived because I didn’t need to check.”
Research consistently shows that ERP changes the way the brain responds to intrusive thoughts in a way that simply talking about the anxiety cannot.
Effective ERP Should Be Evidence-Based and Human
Many people come to us after trying ERP elsewhere with mixed experiences.
Some describe treatment that felt incredibly rigid—sessions focused almost exclusively on anxiety ratings, or feeling as though every question was met with silence out of fear that any response might become reassurance. Others leave believing ERP means being pushed into overwhelming exposures before they feel understood.
That isn’t how we practice.
At Red Elm Psychotherapy, ERP is the foundation of our OCD treatment because it’s the most effective, evidence-based approach we have. But we also believe that healing happens within a strong therapeutic relationship.
That means we take time to understand your story, teach you how OCD works, and collaborate on exposures that are challenging without being overwhelming. We integrate cognitive behavioral strategies and an attachment-informed understanding of relationships while keeping ERP at the center of treatment.
Our goal isn’t to withhold warmth or become emotionally distant. It’s to avoid reinforcing OCD while helping you feel genuinely supported.
You should never have to choose between evidence-based treatment and a therapist who feels human.
What This Looks Like in Real Life
(Note: To protect client confidentiality, the following scenario is a composite case study reflecting common patterns seen in our practice.)
One client came to us after several years of therapy for anxiety. She was thoughtful, self-aware, and had done a lot of work to understand her thoughts. On the surface, it seemed like she “should” have been feeling better by that point.
But her OCD hadn’t changed.
She was still spending hours each day mentally reviewing conversations, trying to determine whether she had said or done something “wrong.” She sought reassurance from loved ones, experienced brief relief, and then quickly found herself back in doubt. Much of her prior therapy had focused on understanding why she felt anxious and processing the distress, which helped her feel supported—but didn’t change the underlying cycle.
When we began ERP, the focus shifted. Instead of trying to solve or analyze the thoughts, she practiced allowing them to be present without engaging in the mental review or reassurance-seeking that followed.
At first, this felt unfamiliar and uncomfortable. Her OCD consistently pushed her toward “figuring it out” the way she always had.
But over time, something important changed: the thoughts didn’t disappear, but they also didn’t pull her into hours of rumination. The urgency softened. The cycle began to lose momentum.
What she described later wasn’t a life without intrusive thoughts—it was a life where she no longer felt trapped in them.
That shift is often what recovery from OCD looks like.
Why Specialized OCD Care Matters Even More During Pregnancy and Postpartum
While finding an OCD specialist is important for anyone with OCD, it becomes especially important during pregnancy and the postpartum period.
Perinatal OCD often involves intrusive thoughts about accidentally or intentionally harming the baby. These thoughts can feel terrifying, especially when they seem completely out of character.
One of the biggest fears we hear from new mothers is: “What if someone thinks these thoughts mean I want to hurt my baby?”
The good news is that intrusive thoughts are actually incredibly common during the perinatal period. For someone with OCD, these thoughts are ego-dystonic—meaning they are unwanted, deeply distressing, and completely inconsistent with who you are as a parent.
Unfortunately, providers without specialized training in perinatal OCD may mistake these symptoms for postpartum anxiety alone, respond with repeated reassurance, or, in rare cases, misunderstand them as postpartum psychosis.
These are very different conditions requiring different treatment approaches.
An OCD specialist understands these differences and knows that ERP can safely and effectively treat perinatal OCD while supporting the unique realities of pregnancy and early parenthood.
The goal isn’t to convince you that you’ll never have another intrusive thought.
The goal is to help those thoughts lose their power, so you can spend more time connecting with your baby and less time trapped in fear.
Questions to Ask When Looking for an OCD Therapist in Northern Virginia
Not every therapist specializes in OCD—and that’s okay. Just like in medicine, different clinicians develop expertise in different areas.
If you’re looking for OCD treatment in Northern Virginia (including Vienna, Mclean, Fairfax, Arlington, or Loudoun County), consider asking potential providers:
What percentage of your practice is dedicated to treating OCD?
Have you received specialized training in Exposure and Response Prevention (ERP)?
What does a typical ERP session look like?
How do you respond when clients seek reassurance during sessions?
Do you regularly treat the specific type of OCD I’m experiencing, such as postpartum OCD, scrupulosity, health OCD, or relationship OCD?
These questions can help you determine whether a therapist has the experience needed to provide evidence-based OCD treatment.
You Don’t Have to Stay Stuck
Living with OCD can be exhausting, but it is also highly treatable.
If you’ve tried therapy before without lasting relief, that doesn’t mean you’ve failed therapy. It may simply mean you haven’t yet received treatment specifically designed for OCD.
At Red Elm Psychotherapy, we provide evidence-based ERP for adults through in-person therapy at our Vienna, VA office and via telehealth throughout the state of Virginia. We also specialize in treating perinatal OCD, helping parents navigate pregnancy and postpartum with compassionate, expert care.
Recovery doesn’t require getting rid of every intrusive thought. It comes from learning that you no longer have to listen to them.
Ready to Take the Next Step?
If you're ready to break the OCD cycle, we are here to walk with you. Click here to schedule a free 15-minute consultation with us today.