

The Birth Story Loop: When “Healthy Baby, Healthy Mom” Isn't Enough
Birth trauma isn't just about what happened in the delivery room—it’s about the mental 'loops' that follow. Dr. Erin Cook explores the intersection of birth trauma and OCD, explaining how a 'clinical emergency' can trigger chronic rumination. Learn how Narrative Therapy and ERP provide a gold-standard path to recovery for postpartum parents.
Sarah had always been a planner. From her college applications to her wedding seating chart, her life was a series of well-executed visions. When she got pregnant, she approached motherhood with that same intentionality. She spent months curating the perfect nursery, researching breast pumps, and eventually, crafting a birth plan that felt like a sanctuary.
She imagined the dim lighting, the specific playlist, and the freedom to move. She was even "rational" about the possibility of a C-section: “As long as we’re both happy and healthy, who cares how the baby comes?” she’d tell herself.
But when Sarah went into labor at 35 weeks, the plan didn't just change—it evaporated.
Suddenly, she wasn't in a dimly lit room with a birth ball; she was hooked to monitors in a sterile high-risk unit. Her blood pressure soared. She was placed on a magnesium drip—a medication that felt like a heavy, searing fog settled over her brain. Her regular doctor was out of town, and the on-call physician seemed to view her birth plan as a list of suggestions rather than her deeply held values.
In that room, the medical team saw a “clinical emergency” to be managed, but Sarah felt like a person being erased. She felt like a vessel for a baby rather than a participant in her own life. That loss of voice—that moment where her “No” or her “Wait” was ignored—became the sharpest edge of the experience.
The Birth of the Loop
A week later, Sarah was home. Her daughter was healthy, and the beautiful nursery was finally in use. But Sarah’s mind was still in that hospital room.
Even though the physical "outcome" was a success, Sarah found herself stuck in what we call the Birth Story Loop. Every time she looked at her daughter, her brain would pivot:
“What if I had rested more in those last few weeks?”
“What if I had advocated harder when the doctor mentioned the induction?”
“Did I fail because I didn't push longer?”
Every time a "perfect" birth announcement popped up on her Instagram feed, she felt a physical pang of jealousy, followed immediately by a wave of shame. She felt like a "bad mom" for not being able to celebrate others, not realizing her brain was simply triggered by the contrast between their agency and her trauma.
Why the Brain Loops: The Unfinished Puzzle
For high-achievers like Sarah, the brain treats a traumatic or disappointing birth like an unsolved puzzle. Because of the magnesium fog and the sheer adrenaline of the emergency, Sarah’s brain didn't get to "record" the birth in a linear way.
It’s like a book with five missing pages in the middle. Her brain keeps looping back to those pages, trying to fill in the blanks of what happened while she was "out of it," hoping that "certainty" will finally bring peace.
In reality, this is rumination—a mental compulsion. The more Sarah "checks" her memories or asks for reassurance from her husband ("Do you think the doctor waited too long?"), the more her brain stays in emergency mode. She isn't processing the birth; she’s re-traumatizing herself through the loop.
How We Break the Loop in Therapy
At Red Elm, we help parents break the loop using a two-pillar approach:
1. Narrative Therapy: Reclaiming the Story We work to externalize the "failure." Sarah didn't fail her birth; she navigated a medical event that went off-script. We move from the toxic positivity of "at least everyone is okay" to the emotional truth of "this was scary, and I am allowed to grieve the experience I didn't get." We help you integrate the disappointment so it becomes a part of your history, rather than a shameful secret.
2. ERP: Stopping the Compulsions Exposure and Response Prevention (ERP) is the "gold standard" for the anxiety and OCD that often follows a difficult birth.
The "Response Prevention": We identify the reassurance-seeking (the googling, the constant asking of a partner) and practice sitting with the discomfort of not knowing for sure.
The "Exposure": We might write out the "scariest version" of the birth story and read it together until the "shiver" it sends down your spine begins to habituate.
Beyond “Healthy”
If you find yourself stuck in a birth story loop, know that your disappointment isn't ungratefulness. It is a sign that your brain is trying to make sense of a moment where you lost your agency.
Therapy isn’t about changing what happened in that hospital room. But we can stop the birth from "happening" to you every single day in your head. It’s time to reclaim your energy for the life you’re building now.
Reach out now to stop the birth story loop.
About the Author
Dr. Erin Cook is a clinical psychologist and co-founder of Red Elm Psychotherapy, a Virginia-based practice specializing in perinatal mental health and OCD.
She works with women navigating the complexities of pregnancy, postpartum, and early motherhood—specializing in those moments when anxiety or intrusive thoughts feel overwhelming or out of character. Her approach to treating birth trauma is collaborative, thoughtful, and grounded in helping clients understand the "why" behind their brain’s loops so they can finally feel less alone in their experience.

When Insight Isn’t Enough: Why OCD Still Feels So Convincing
You know the thought is irrational, yet five minutes later you're back in the loop. The problem isn't a lack of logic—it’s an excess of it. Discover why your intelligence is being weaponized against you and how to finally 'drop the rope' in the mental tug-of-war.
You know the thought doesn’t make sense. You’ve analyzed it from every angle. You’ve checked the facts. You’ve reassured yourself.
Maybe you’ve even had a moment where you thought: “Okay. This is definitely Obsessive-Compulsive Disorder (OCD).”
And then five minutes later, the anxiety comes rushing back. Your stomach drops. The doubt feels real again. And suddenly you’re back in the loop trying to solve it one more time.
If this happens to you, you are not failing at being rational. In fact, many people with OCD are exceptionally intelligent, analytical people. That’s part of what makes OCD so convincing.
OCD Turns Intelligence Against You
In most areas of life, thinking harder helps. Being responsible and paying attention to details are traits that probably helped you succeed in school, work, or parenting.
But OCD hijacks those same strengths. Instead of using your mind to solve real-world problems, OCD pulls you into impossible ones:
“What if I secretly meant that thought?”
“What if I’m missing something important?”
“What if I can never be fully certain?”
At some point, the thinking itself becomes the compulsion. Not because you’re irrational, but because your brain is desperately trying to make the anxiety stop.
What Mental Compulsions Actually Look Like
A lot of people imagine OCD as visible checking or hand washing. But many compulsions happen entirely inside your head. From the outside, you may look calm. Inside, you are exhausted.
You might spend hours replaying conversations, reviewing memories, or checking whether a feeling "feels true." Depending on what you value most, these loops can take many forms:
Relationship OCD (ROCD): Constantly analyzing your partner or your feelings to "prove" you are in the right relationship.
Perinatal OCD: Intrusive, terrifying thoughts about the safety of your baby and the constant mental checking that follows.
Scrupulosity: A painful loop of moral or religious doubt, where you feel you must constantly "fix" your standing with God or your conscience.
The OCD Cycle: The universal engine that keeps all these themes running on a loop.
Why Insight Alone Doesn’t Stop OCD
One of the most painful parts of OCD is that you likely already know your fears are irrational. Insight is not the problem. You can understand OCD intellectually and still feel trapped by it emotionally because OCD is not a logic problem; it’s an alarm system problem. Your brain sends out a false signal of danger, and your mind works overtime to explain why the danger feels so real. Unfortunately, the more seriously you treat the thought—by analyzing or researching it—the more important your brain believes it must be.
The Tug of War
Imagine you are standing at the edge of a canyon. On the other side is a monster representing your intrusive thoughts. Between you is a rope.
The moment an intrusive thought appears, the monster yanks the rope. Instinctively, you pull back. You try to prove the thought wrong or get certainty. But the harder you pull, the more consumed you become by the fight. Soon, your entire life revolves around the rope.
ERP Is About Leaving the Fight
This is where Exposure and Response Prevention (ERP) changes things. ERP is not about proving the intrusive thought false or "thinking more rationally."
ERP helps you learn how to stop engaging with the struggle altogether. Whether you are dealing with harm OCD, contamination fears, or the constant "background noise" of uncertainty, the goal is not to defeat the monster; the goal is to stop organizing your life around it.
What “Dropping the Rope” Looks Like:
ERP teaches you to practice allowing uncertainty to exist.
That might mean:
Allowing a scary thought to stay without analyzing it.
Resisting the urge to mentally review your day.
Noticing anxiety without trying to "neutralize" it.
At first, this feels deeply uncomfortable. It feels irresponsible to let the "what if" go unanswered. But over time, your brain learns the truth: The thought itself was never the danger.
Here is the problem with doing this alone: Your brain is convinced that the rope is the only thing keeping you safe. It tells you that if you let go, the monster wins, or something terrible will happen. Dropping the rope feels like an act of negligence.
This is one of my main roles in guiding clients through [Exposure and Response Prevention (ERP)]: to stand at the edge of that canyon with you. I help you tolerate the "itch" to pull back until your brain finally learns that the monster can’t actually cross the canyon—whether you hold the rope or not.
A 30-Second Exercise: Practice the Pause
You don’t have to drop the rope forever right this second. Today, just practice delaying the pull.
Next time you feel that jolt of anxiety and the urge to "figure it out" or check a memory hits:
Acknowledge the rope: Say to yourself, "OCD just threw me the rope."
Set a timer for 30 seconds: Do not analyze, do not Google, and do not replay the memory for just thirty seconds.
Feel the tension: Notice the discomfort in your body without trying to fix it.
Even if you go back to the loop after those 30 seconds, you’ve just proven something huge: You are the one in control of your hands, even when the anxiety is loud.
You Don’t Need More Insight. You Need a Different Response.
Many people who reach out for OCD treatment are already highly self-aware. They’ve read the articles; they can explain the cycle better than anyone. But they still feel trapped.
Recovery doesn't happen through more analysis. It happens through learning a different relationship with fear.
OCD Therapy in Virginia
I work with adults struggling with OCD, intrusive thoughts, rumination, and mental compulsions using evidence-based ERP therapy.
Together, we focus on helping you step out of the exhausting mental loops so you can spend less time trapped in your head and more time fully engaged in your life.
Ready to drop the rope?
About the Author
Dr. Niles Cook is a licensed clinical psychologist and co-founder of Red Elm Psychotherapy. He specializes in helping high-achieving adults and professionals who are exhausted by the "intelligence trap"—where the same analytical skills that made them successful are now being used by OCD to keep them stuck in cycles of doubt.
Using Exposure and Response Prevention (ERP), Dr. Cook provides a structured, no-nonsense path for clients to stop over-analyzing their lives and start living them. His approach is direct, collaborative, and designed for those who need more than just insight—they need a different way to respond to fear.
Dr. Cook provides specialized telehealth therapy across the state of Virginia.
Note: This content is educational and does not constitute medical advice or a therapist-client relationship. If you are in a crisis, please call 988 or go to the nearest emergency room.

Why Your Relationship Feels Different After a Baby — Especially When Anxiety or OCD Is Involved
Some couples don’t fight more after a baby.
Instead, things start to feel… off.
You’re functioning. You’re getting through the day. But something in the relationship feels quieter, more distant—and harder to explain.
For many high-functioning women, anxiety and intrusive thoughts don’t just stay internal. They subtly reshape how you show up with your partner.
Some couples don’t fight more after they bring their baby home. They aren’t having dramatic arguments or obvious problems. But somewhere between the diapers and the sleepless nights, something shifts.
Things don’t feel bad—just… off.
There’s a little more distance. A little less ease. You might find yourself feeling less connected to the person you just started a family with—and you aren't entirely sure why.
For many women, this shift is compounded by anxiety, intrusive thoughts, or patterns that feel difficult to explain—especially during pregnancy or the postpartum period. If you’re having thoughts that feel disturbing, out of character, or hard to talk about—you are not alone. This is something we treat often at Red Elm Psychotherapy.
When Anxiety Becomes a Third Partner
When anxiety or OCD is present, the relationship often becomes one of the primary places it gets expressed. This can show up as general anxiety, intrusive thoughts, or more defined OCD patterns—but the impact on the relationship often feels the same.
Anxiety is driven by a need for certainty. In a partnership, that often translates into:
Constant Scanning: Checking your partner’s face or tone for signs of frustration, boredom, or distance.
Reassurance Seeking: Asking the same questions repeatedly to soothe a “sticky” thought (e.g.,“Is the baby breathing?” or "Are we okay?" ).
Over-Responsibility: Feeling like you must carry the entire emotional or physical load to prevent something “bad” from happening.
Hypersensitivity: Interpreting a neutral moment—like a quiet dinner or a short text—as a sign that the relationship is failing.
These thoughts are unwanted, distressing, and often completely out of character. They are not a reflection of your intentions or the quality of your bond. We go into more detail about how this pattern works on our Perinatal OCD page.
Sometimes, the anxiety begins to focus on the relationship itself. This is often referred to as Relationship OCD (ROCD), where “sticky” thoughts lead you to constantly question your partner’s “rightness” or search for flaws as a way to reach a certainty that doesn’t exist.
The Reassurance Loop: The Unwitting Accomplice
In high-functioning couples, partners are often incredibly kind and helpful. However, that kindness can unintentionally feed the anxiety.
In the world of OCD, this is called accommodation—when a partner’s well-intentioned efforts to reduce your distress actually keep the anxiety cycle spinning. Many people feel ashamed of how much reassurance they need and worry about "burdening" their partner.
A partner may provide reassurance, engage in repetitive “what-if” conversations, or try to become the "solution" to intrusive thoughts. The relationship starts to function as a tool for resolving anxiety. It works briefly, but the relief never lasts. Over time, this creates a painful cycle of tension, resentment, and loneliness—even when you’re sitting right next to each other.
The High-Functioning Mask
For many of the couples we see in Vienna and across Northern Virginia, everything looks fine from the outside. You are showing up. You look responsible. You are getting the job done.
You may be caring for a baby, managing a household, or returning to work—all while internally feeling overwhelmed or disconnected. But behind closed doors, there can be a deep sense of isolation. You aren’t “bad at communicating”—you’re navigating a system under sustained strain.
It’s Not Broken—It’s Under Strain
If this feels familiar, it doesn’t mean you picked the wrong partner or that your relationship is broken. It often means your relationship has been pulled into a cycle of anxiety.
The solution isn’t simply to “communicate better.” It’s understanding how you relate to each other through the lens of anxiety—and how certain patterns, even the ones born out of love, can keep both of you stuck.
How Therapy Helps
Therapy can help separate the anxiety from the relationship. Through structured, evidence-based approaches—including Exposure and Response Prevention (ERP) when appropriate—treatment focuses on:
Separating the anxiety from the person: Understanding that intrusive thoughts are not a reflection of who you are.
Reducing reassurance loops: Learning how to support each other without reinforcing the cycle.
Rebuilding steadiness: Moving away from reactive patterns and back toward the values that brought you together.
You don’t have to keep feeling "off." Understanding the pattern is often the first step toward feeling more like yourselves again.
Ready to Take the Next Step?
If your anxiety feels constant, intrusive, or difficult to step out of—especially during pregnancy or after having a baby—it may be more than something to simply "push through."
We specialize in helping women navigate postpartum anxiety, intrusive thoughts, and OCD. We use structured, evidence-based treatment designed to help you step out of the loop and feel more like yourself again.
We offer in-person sessions in Vienna, VA and work with clients across Virginia via telehealth, including McLean, Arlington, and the surrounding Northern Virginia area.
About the Author
Dr. Erin Cook, PsyD is a licensed clinical psychologist and co-founder of Red Elm Psychotherapy, a Virginia-based practice specializing in perinatal mental health and OCD. She works with women navigating pregnancy, postpartum, and early motherhood—particularly when anxiety or intrusive thoughts feel overwhelming or out of character.

Scrupulosity OCD: Why You Feel Like a Bad Person (Even When You’re Not)
“What if I’m actually a bad person and just don’t realize it?”
Scrupulosity OCD often sounds like this—and the more you try to figure it out, the more stuck you feel.
To others, you’re the responsible one. Thoughtful. Conscientious. Someone who cares deeply about doing the right thing.
But internally, it feels very different.
Your mind won’t stop asking:
Did I just lie?
Did I accidentally hurt someone?
What if I’m actually a bad person and don’t realize it?
You replay conversations. You analyze your intentions. You look for a feeling—some indication—that you’re “okay.”
And it never quite lands.
And even asking these questions can feel uncomfortable—like maybe it says something about who you are.
If your mind feels like a constant courtroom—evaluating, questioning, trying to reach a verdict—this may be Scrupulosity OCD, a specific subtype of OCD centered on morality, responsibility, and fear of being a bad person.
What Scrupulosity OCD Actually Is
Scrupulosity OCD is a form of obsessive-compulsive disorder (OCD) where intrusive doubts attach to morality, ethics, or religion.
At its core, this isn’t a problem with your values—it’s how your brain is responding to doubt about them.
Most people can tolerate some ambiguity about whether they handled something perfectly. They can think, “That might not have been ideal,” and move on.
OCD doesn’t allow that.
It demands something impossible:
“I need to know for sure that I am a good person.”
And because that kind of certainty doesn’t exist, the doubt never resolves.
What It Looks Like in Real Life
Scrupulosity OCD often looks like “being a good person”—just taken to a painful extreme. These patterns aren’t personality traits—they’re compulsions, attempts to reduce anxiety and feel certain.
You might notice:
Mentally replaying interactions to make sure you didn’t say something wrong or misleading
Compulsive confession or reassurance-seeking (“I need to tell them what I thought just in case”)
Over-apologizing for things that didn’t actually harm anyone
Internal checking (“Do I feel like a good person right now?”)
Decision paralysis around “ethical” choices (even small ones)
Researching or analyzing to prove you did the “right” thing
This can also show up in relationships, where doubt and responsibility feel especially high.
The intention is to feel certain.
The result is the opposite.
When Scrupulosity OCD Shows Up in Sexuality and the Body
For some individuals—especially those with a religious or high-moral framework—scrupulosity OCD extends into questions about sexuality, purity, and whether something is “right” or “wrong” in intimate relationships.
This can look like:
Persistent doubts about whether sexual thoughts, desires, or behaviors are immoral or “sinful”
Mentally reviewing intimate experiences to determine if something crossed a line
Seeking reassurance (from a partner, internally, or from a religious framework) about whether something was “okay”
Avoiding intimacy due to fear of doing something wrong
Feeling intense guilt, anxiety, or “moral distress” during or after sexual experiences
Over time, this doesn’t just stay in your thoughts—it can begin to affect the body.
Clinically, we often see:
Increased muscle tension, particularly in the pelvic floor
Difficulty relaxing during intimacy
Pain with sex that is worsened by anxiety and hypervigilance
A reinforcing cycle where physical discomfort increases fear, and fear increases physical tension
This isn’t just about beliefs or a lack of information.
It’s OCD attaching to something deeply meaningful and trying to eliminate uncertainty—using both the mind and body to do it.
This is an area where collaborative care can be especially important. When anxiety, guilt, or intrusive thoughts are contributing to muscle tension, pain, or difficulty with intimacy, working across disciplines can make a real difference.
We often coordinate care with providers supporting reproductive, sexual, or physical health to address both the psychological and physical patterns at the same time. Addressing one without the other often leaves the cycle intact.
The OCD Loop
Like all forms of OCD, scrupulosity follows a predictable cycle:
The Thought:
“What if I did something wrong?”
The Anxiety:
A surge of guilt, dread, or moral discomfort
The Compulsion:
Replaying, confessing, apologizing, researching, checking
The Relief:
Temporary—brief, incomplete
The Return of Doubt:
“But what if that wasn’t enough?”
The more you try to prove you’re a good person, the more uncertain you feel.
If this cycle feels familiar, you can read more about how OCD reinforces itself here.
Why Scrupulosity OCD Gets Missed
Scrupulosity OCD is often overlooked because the content of the thoughts sounds reasonable.
Who wouldn’t want to be honest, ethical, or kind?
Because of this, these patterns are often reinforced instead of recognized as OCD. You might even be praised for being conscientious or thoughtful.
But there’s an important difference between values and OCD:
Values guide behavior
OCD demands certainty and creates distress
This isn’t about becoming a better person or getting it exactly right. It’s about a brain that won’t let uncertainty settle.
Why This Can Feel So Distressing
For many people, this isn’t just anxiety—it feels like something deeper.
It can feel like:
“What if this means something about who I am?”
“What if other people would see me differently if they knew?”
“What if I can’t trust myself?”
That’s part of what makes scrupulosity OCD so painful.
It doesn’t just create doubt—it targets your sense of identity.
What Scrupulosity OCD Is NOT
It’s not:
Just being conscientious or thoughtful
A sign that you’re actually doing something wrong
A moral or character flaw
Something you can solve by thinking harder or trying to be “better”
If anything, people with scrupulosity tend to hold themselves to exceptionally high internal standards.
How ERP Therapy Treats Scrupulosity OCD
The way out of Scrupulosity OCD is not becoming more certain, more ethical, or more perfect.
It’s learning to stop responding to the doubt as if it needs to be solved.
This often feels counterintuitive at first—especially if you’re used to trying to “get it right.”
Exposure and Response Prevention (ERP)—the gold-standard treatment for OCD—focuses on changing your relationship to uncertainty.
This includes:
Reducing compulsions
Not confessing, not over-apologizing, not mentally reviewingAllowing uncertainty
Practicing responses like:
“Maybe I did something wrong. Maybe I didn’t.”Acting based on values, not fear
Making decisions without needing absolute certainty first
Over time, your brain learns something essential:
You don’t need certainty to move forward.
Who Experiences Scrupulosity OCD?
Scrupulosity often shows up in people who are:
Thoughtful and introspective
Highly responsible
Holding themselves to high internal standards
It can also become more intense during major life transitions.
We often see this during pregnancy and postpartum, when the pressure to be a “good” parent or make the “right” decisions feels especially high. Intrusive doubts about whether you are doing enough—or doing something wrong—can take on an obsessive, persistent quality.
A Final Thought
If this sounds familiar, it’s not because you’re a bad person.
It’s because your brain is over-sensitive to doubt—and keeps trying to solve something that can’t be solved by certainty.
Scrupulosity OCD is a treatable condition, not a reflection of who you are.
You don’t have to keep proving, over and over again, that you’re a good person.
You’re allowed to live your life without reaching a final answer.
Next Step
If you’re noticing this pattern, working with a therapist trained in OCD and ERP therapy can make a meaningful difference.
At Red Elm Psychotherapy, we specialize in treating OCD—including scrupulosity—using structured, evidence-based approaches designed to actually break the cycle.
Schedule a consultation to get started.
About the Author
Dr. Niles Cook is a licensed clinical psychologist and co-founder of Red Elm Psychotherapy. He specializes in the treatment of obsessive-compulsive disorder (OCD), including scrupulosity and other forms of intrusive doubt, using Exposure and Response Prevention (ERP).
Dr. Cook works with high-achieving adults and professionals who feel stuck in cycles of overthinking, uncertainty, and the need to get things exactly right. His approach is structured, direct, and grounded in evidence-based treatment.
He provides telehealth therapy across Virginia and is listed with the International OCD Foundation.

Why Your Postpartum Anxiety Feels So Intense (And What Might Actually Be Going On)
Postpartum anxiety can feel constant, physical, and hard to turn off. But when worries become intrusive, repetitive, or terrifyingly out of character, something more specific may be happening: postpartum OCD. Learn how to tell the difference — and why evidence-based treatment can help.
You expected motherhood to be hard.
You knew you’d worry about new things and have new responsibilities.
What you didn’t expect was how constant—and how physical—it would feel.
How hard it would be to turn your mind off.
Anxiety after birth is incredibly common. As many as 1 in 5 new moms experience clinically significant postpartum anxiety.
These worries often feel understandable—grounded in real, day-to-day concerns like:
“Is my baby eating enough?”
“What if they’re not gaining weight?”
“What if something happens while they’re sleeping?”
“Am I doing this right?”
“What if I miss a sign that something is wrong?”
These fears are usually future-focused and tied to the very real responsibility of caring for a new baby. They may ease (even temporarily) with reassurance, and tend to come and go depending on what’s happening in the moment.
But for some moms, the anxiety starts to feel different.
Not just constant—but more intrusive.
More unsettling.
Harder to brush off.
When that happens, there’s often something more specific going on.
When Postpartum Anxiety Becomes Something More Intrusive
Although many women experience postpartum anxiety, a smaller subset—around 3–5% of new moms—experience thoughts that become more intense, repetitive, and difficult to dismiss.
This is often what we call postpartum OCD.
With postpartum OCD, the thoughts don’t just feel like worries—they feel intrusive and unwanted.
They can feel completely out of character, almost like they don’t belong to you.
They tend to be sticky, repetitive, and hard to let go of.
Common intrusive thoughts can include:
“What if I stab my baby?”
“What if I drop them on purpose?”
“What if I sexually harm my baby?”
“What if I snap and lose control?”
“What if I already did something and didn’t realize it?”
These thoughts are upsetting not just because of what they say—but because they feel so unlike you.
That’s exactly why they feel so terrifying.
That disconnect can create an intense sense of fear and shame, making it hard to talk about or even acknowledge what’s happening.
Another important difference is that reassurance doesn’t actually bring lasting relief.
Instead, it pulls you into a cycle of needing more and more certainty—which can make the thoughts feel even stronger over time.
To cope, many moms find themselves:
Avoiding being alone with their baby
Mentally reviewing or checking what they’ve done
Repeatedly seeking reassurance
Even though these strategies make sense in the moment, they can unintentionally keep the cycle going.
A Simple Way to Understand the Difference
For many new parents, anxiety sounds like:
“What if something happens to my baby?”
But when the thoughts shift, they can start to sound more like:
“What if I’m the one who causes harm?”
That shift—from fear of something happening to your baby, to fear of something happening because of you—is often the point where things begin to feel much more intense.
Why This Matters
Many women are told they’re “just anxious,” and try to cope by thinking through the thoughts, reassuring themselves, or avoiding anything that feels risky.
But when these thoughts are part of OCD, those strategies can actually keep the cycle going.
The good news is that there is a highly effective, evidence-based treatment that helps break this pattern.
This is exactly what Exposure and Response Prevention (ERP) is designed to target—helping you step out of the reassurance cycle and retrain your brain’s response to these thoughts.
You Don’t Have to Stay Stuck in This
If your anxiety feels constant, intrusive, or hard to turn off, this is something we treat every day.
You don’t have to keep managing this on your own.
We specialize in helping new mothers work through intrusive thoughts and anxiety using evidence-based treatment—so you can get out of the loop and feel like yourself again.
We offer in-person sessions in Vienna, VA and work with clients across Virginia via telehealth, including those in McLean and the surrounding Northern Virginia area.
About the Author
Dr. Erin Cook is a clinical psychologist and co-founder of Red Elm Psychotherapy, a Virginia-based practice specializing in perinatal mental health and OCD. She works with women navigating pregnancy, postpartum, and early motherhood—especially when anxiety or intrusive thoughts feel overwhelming or out of character.
Her approach is collaborative, thoughtful, and grounded in helping clients understand what they’re experiencing and feel less alone in it.

Relationship OCD: Why You Can’t Stop Doubting Your Relationship
Relationship OCD can make normal doubt feel urgent, dangerous, and impossible to let go of. Learn how ROCD traps you in checking, comparison, reassurance-seeking, and “what if” loops — and how ERP therapy can help.
“What if I don’t actually love them?”
“What if I’m making a huge mistake?”
“Why am I constantly overanalyzing every single thing they say or do?”
Most people experience moments of doubt in a relationship. But for some, these questions don’t just pass—they loop. They intensify. They become a background noise that never truly shuts off, eventually taking over your daily life and your ability to enjoy your partner.
If your relationship feels less like a partnership and more like a puzzle you are desperately trying to "solve," you might be experiencing Relationship OCD (ROCD).
What Is Relationship OCD?
ROCD is a common subtype of Obsessive-Compulsive Disorder. It isn’t a sign that your relationship is "wrong" or that you’ve fallen out of love. Instead, it is a cycle driven by a low tolerance for uncertainty.
While everyone has fleeting doubts, someone with ROCD feels an urgent, crushing need for 100% certainty about their feelings, their partner’s flaws, or their long-term compatibility. Because perfect certainty is impossible to find, the brain stays stuck in a loop of searching for it.
Common Signs of ROCD
ROCD usually manifests through intrusive thoughts (obsessions) and the actions you take to quiet them (compulsions). You might find yourself:
Mentally Checking: Constantly asking yourself, "Do I feel 'the spark' right now?" while kissing or hanging out.
Comparing: Obsessively comparing your partner’s traits or your relationship to friends, exes, or even fictional characters.
Reassurance Seeking: Asking friends, family, or even your partner if you "seem" happy or if the relationship looks "right" to them.
Researching: Spending hours on forums or reading articles trying to find a definitive "sign" that you should stay or leave.
Hyper-fixating on Flaws: Becoming consumed by a partner’s physical "imperfections" or minor personality quirks as evidence that they aren't "The One."
Why It Feels So Real
The paradox of OCD is that it targets what you value most. If you didn’t care about your partner or the concept of love, your brain wouldn't bother using these thoughts to scare you.
Furthermore, ROCD exploits the fact that human emotions are naturally fluid. We don’t feel "madly in love" every second of every day. To an ROCD brain, a slight dip in affection isn't just a normal part of a Tuesday—it’s viewed as an emergency that must be analyzed immediately.
ROCD vs. Normal Doubt
How do you know if you're in the wrong relationship or if you just have OCD?
Normal Doubt
Comes and goes; usually triggered by specific, real-world issues.
Doesn't usually result in hours of "mental work" or research.
You can focus on other parts of your life (work, hobbies).
Feelings are generally stable despite the doubt.
Relationship OCD
Persistent, intrusive, and urgent.
Leads to repetitive compulsions to ease anxiety.
The doubt feels like a "cloud" over everything you do.
Feelings feel "gone" because anxiety is suppressing them.
The Cycle of ROCD
ROCD thrives on a specific loop:
The Trigger: A thought or feeling (e.g., “I didn’t miss them today”).
Anxiety: A spike of fear or "urgency" to figure out what that means.
Compulsion: You Google "signs of falling out of love" or check your feelings.
Temporary Relief: You feel better for a moment because you found an answer.
The Repeat: The doubt returns, and you need a stronger "fix."
There is a Way Out
The goal of therapy isn't to prove that your relationship is perfect—it’s to help you live comfortably with the fact that no relationship is certain.
Exposure and Response Prevention (ERP) is the gold standard for treating ROCD. It helps you break the cycle by teaching your brain that you don't have to "answer" every intrusive thought that pops into your head. You can learn to experience a doubt without letting it dictate your actions.
You don’t need to end your relationship to get relief, and you don’t need to reach 100% certainty before you start feeling better.
Take the Next Step
If this cycle feels familiar, you don’t have to keep trying to figure it out on your own. Our specialists are trained in evidence-based tools to help you reclaim your life from the "What Ifs."
Explore our Relationship OCD Service Page
Learn more about OCD Therapy
HowERP Therapyworks
You deserve to be present in your life, rather than stuck in your head.
About the Author
Dr. Niles Cook, PsyD is a licensed clinical psychologist and co-founder of Red Elm Psychotherapy. He specializes in the treatment of obsessive-compulsive disorder (OCD) and anxiety using Exposure and Response Prevention (ERP). Dr. Cook works with high-achieving adults and professionals who feel stuck in cycles of overthinking, doubt, and perfectionism. He provides telehealth therapy across Virginia. He is listed with the International OCD Foundation.

Postpartum Anxiety in Vienna, VA: What It Feels Like and How to Get Help
Postpartum anxiety can look like responsibility from the outside—but inside, it can feel constant, physical, and exhausting. Learn what postpartum anxiety feels like, when it may overlap with OCD, and how therapy in Vienna, VA can help.
Many women in Vienna and Northern Virginia are surprised by how intense postpartum anxiety can feel. You may have expected to feel joy, relief, or fulfillment after your baby arrives—but instead, you feel on edge, constantly scanning for something that could go wrong.
If anxiety has started to shape your experience of motherhood, you’re not alone—and support is available.
What Postpartum Anxiety Actually Feels Like
Anxiety after your baby arrives can change how it feels to be a mother, a partner, a friend—even yourself.
Many women notice that anxiety begins to interfere with their ability to connect with their baby or their spouse. It can feel like your mind is always “on,” even when you want to rest.
Common experiences include:
racing thoughts that are hard to slow down
constant checking (your baby’s breathing, safety, positioning)
difficulty relaxing, even when things are calm
sleep disruption—even when your baby is sleeping
For some women, these patterns begin to form a cycle of checking, reassurance, or mental reviewing that can overlap with perinatal OCD.
Why It’s So Confusing
Many of the women we work with are used to having it together. You’re thoughtful, prepared, capable.
And then suddenly, at a moment when you expected to rely on those strengths, something feels different.
You may still be functioning—taking care of your baby, managing your responsibilities—but internally, it feels like you’re working much harder just to get through the day.
Part of what makes postpartum anxiety so confusing is that it can look like responsibility.
This is especially true for women who are used to performing at a high level in other areas of their lives.
It can feel like:
“I’m just being careful”
“I should be thinking about this”
“This is what a good mom does”
But over time, the constant vigilance becomes exhausting.
Postpartum Anxiety vs. Postpartum OCD
Sometimes postpartum anxiety includes intrusive thoughts that feel disturbing or out of character.
When this happens, it can be helpful to understand the difference between anxiety and OCD.
With anxiety, thoughts often sound like:
“What if something happens to my baby?”
With OCD, thoughts may sound like:
“What if I cause something to happen to my baby?”
These thoughts are typically ego-dystonic—meaning they feel completely out of line with who you are.
When anxiety becomes paired with repetitive checking, reassurance-seeking, or mental reviewing, it may be part of a pattern of perinatal OCD.
Why It Keeps Going
One of the hardest parts of postpartum anxiety is that the things that help in the moment often keep the cycle going over time.
For example:
You check → anxiety decreases
You avoid something → anxiety decreases
You seek reassurance → anxiety decreases
Your brain learns:
👉 “This must be important—we need to keep doing this.”
Over time, this reinforces the cycle.
The problem isn’t the thoughts themselves.
It’s how your brain has learned to respond to them.
When to Get Help
You don’t have to wait until things feel unmanageable.
Many women reach out when they notice:
feeling anxious more often than not
difficulty relaxing, even when trying strategies that used to help
ongoing sleep disruption
difficulty feeling connected to their baby
feeling stuck in cycles of worry, checking, or mental loops
Postpartum Anxiety Therapy in Vienna, VA
We provide therapy for postpartum anxiety in Vienna, Virginia, and work with clients throughout Northern Virginia and across the state via telehealth.
Treatment is structured, collaborative, and grounded in evidence-based approaches that help reduce anxiety while supporting you in reconnecting with your life and your role as a parent.
If this resonates, you can reach out to schedule a consultation.
About the Author
Dr. Erin Cook is a clinical psychologist and co-founder of Red Elm Psychotherapy, a Virginia-based practice specializing in perinatal mental health and OCD. She works with women navigating pregnancy, postpartum, and early motherhood—especially when anxiety or intrusive thoughts feel overwhelming or out of character.
Her approach is thoughtful, collaborative, and grounded in helping clients feel less alone in what they’re experiencing.

Why ERP Feels So Hard (And Why That Means It’s Working)
You know the thoughts don’t make sense—but they still feel urgent. This is why ERP feels so hard, and why that discomfort is actually part of getting better.
If you’re reading this, you probably already know that your intrusive thoughts don’t make sense. You know the logic is flawed. You know that checking the stove for the fifth time or replaying that conversation in your head won’t actually change the outcome.
Logic isn't the problem.
The problem is that these thoughts feel urgent, important, and impossible to ignore. They don't feel like "just thoughts"—they feel like fires that need to be put out right now.
The Loop You’re Stuck In
Most people try to think their way out of OCD. You analyze. You Google. You seek reassurance from your partner. You replay the "evidence" over and over.
And for a second, it works. The anxiety dips. You feel a brief moment of "certainty."
But then the doubt creeps back in. “But what if I missed something? What if this time is different?” This is the OCD cycle of Obsession → Compulsion → Temporary Relief. Every time you perform a compulsion to feel safe, you are accidentally teaching your brain that the "threat" was real. You are feeding the monster to keep it quiet, but the monster only gets hungrier.
Reclaiming Your Brain: What ERP Actually Is
Most clinical descriptions of Exposure and Response Prevention (ERP) make it sound like a chore. In reality, ERP is a rebellion. ERP is not about "getting rid of thoughts." (Spoiler: you can't control what pops into your head). It’s about changing your relationship to those thoughts. It means doing the exact opposite of what your brain is screaming at you to do.
What ERP Feels Like in Practice:
Letting a thought sit in your mind without trying to "answer" it or solve it.
Resisting the urge to check—whether that’s a door lock, a physical sensation, or a memory.
Staying in the discomfort of uncertainty instead of chasing the high of reassurance.
Why It Feels "Wrong"
Here is the truth that most textbooks won't tell you: Doing ERP feels irresponsible.
When you stop performing your compulsions, your brain will tell you that you’re being careless. It will tell you that you’re ignoring something dangerous. It will feel like you are walking a tightrope without a net.
That feeling? That’s the feeling of your brain re-wiring itself. If it feels "right" and comfortable, you aren't doing ERP. When it feels risky and uncertain, you are finally interrupting the cycle that has kept you stuck for years.
Is ERP Therapy Hard?
Because ERP is the "gold standard" for OCD treatment, people often ask if the process is as intense as it sounds. The short answer is: Yes, ERP is hard because it requires you to intentionally lean into uncertainty rather than running away from it.
However, "hard" doesn't mean "reckless." In our practice, we don't throw you into the deep end. We use a fear hierarchy to help you face challenges in a structured way. The goal isn't just to be "brave"—it’s to retrain your brain's alarm system so that eventually, the things that feel impossible today become background noise.
Stop Analyzing. Start Living.
OCD thrives on the "What If." ERP thrives on the "So What?" By leaning into the uncertainty, you stop being a prisoner to your own thoughts. You stop managing your anxiety and start living your life again.
By leaning into the uncertainty, you stop being a prisoner to your own thoughts. You stop managing your anxiety and start living your life again.
Dr. Niles Cook specializes in treating OCD using evidence-based Exposure and Response Prevention (ERP). He works with adults across the full spectrum of OCD presentations, helping them move past the "mental loops" and back into the driver’s seat.
If this feels familiar, you don’t have to keep managing it alone.
We offer evidence-based OCD treatment for adults across Virginia.
If you’re experiencing this during pregnancy or postpartum, you can learn more about our postpartum and perinatal therapy here.

Why Do Intrusive Thoughts Feel So Real Postpartum?
Intrusive thoughts after having a baby can feel frighteningly real. This post explains why postpartum intrusive thoughts happen, what they mean, and how to begin stepping out of the cycle.
An intrusive thought can be easy to recognize as irrational—and still feel completely convincing.
You might think, I know I don't want this to happen. I know this is just a thought. So why does it feel like a warning?
This is one of the most confusing parts of postpartum anxiety and OCD. The distress often isn't just what you thought. It's the feeling that the thought must mean something because of how strongly your mind and body reacted to it.
Understanding that distinction can make intrusive thoughts feel much less mysterious.
When a Thought Feels Like a Warning
Our brains are constantly deciding what deserves attention. Most thoughts pass through without much notice. But when a thought is connected to something you care deeply about—especially your baby's safety—it can trigger a much stronger response.
The brain essentially asks:
Could this matter? Could something go wrong? Do I need to do something about it?
If the answer feels even slightly uncertain, your attention may lock onto the thought.
You might notice:
a rush of anxiety or dread
a strong physical reaction
an urge to mentally review what happened
a feeling that you need to figure out what the thought means
difficulty letting the thought go
The intensity of that reaction can make the thought seem more significant than it actually is.
This is one reason an intrusive thought can feel real without being true.
Your Brain Can Confuse Importance With Danger
One reason intrusive thoughts become so convincing is that the brain tends to treat importance and danger as closely related.
If something feels important, your brain wants you to pay attention to it.
And after having a baby, there is plenty that feels important.
You are responsible for another person's safety. You may be watching your baby closely, anticipating their needs, and constantly making decisions about what is safe. Your brain is naturally more tuned in to possible threats.
That heightened vigilance can be useful.
But it can also mean that an unlikely possibility suddenly gets the same level of attention as a realistic concern.
A thought like:
What if something terrible happened?
can start to feel less like a mental event and more like a problem that needs to be solved.
Why Anxiety Makes Thoughts Feel More Believable
Anxiety doesn't necessarily make you believe a thought intellectually. Instead, it can make the thought feel important enough that you can't dismiss it.
This is an important distinction.
You may consciously know:
“I don't actually believe this is going to happen.”
while another part of your brain is responding:
“But what if? You should probably make sure.”
That second response is often what keeps the thought alive.
The more attention you give the thought, the more familiar and noticeable it becomes. The more frightening it feels, the more important it seems. And the more important it seems, the harder it becomes to leave it alone.
This can create a frustrating loop:
Intrusive thought → anxiety → “Why did I think that?” → increased attention → thought feels more significant → more anxiety
The problem isn't that you failed to reassure yourself enough.
The problem is that your brain has learned that the thought deserves investigation.
Why Postpartum Intrusive Thoughts Can Feel Especially Convincing
The postpartum period creates a particularly powerful environment for this process.
You may be:
sleeping less than usual
physically recovering from birth
adjusting to a new identity
responsible for a completely dependent baby
navigating feeding or medical concerns
more aware than ever of potential dangers
experiencing major changes in your relationships and routines
When your nervous system is already on high alert, it can be harder to recognize a thought as simply a thought.
You may find yourself thinking:
“I wouldn't normally think this. Why am I thinking it now?”
or:
“If my brain came up with this, maybe there's a reason.”
That second question is where many women get stuck.
The presence of a thought does not tell you why it appeared. And the intensity of your reaction does not tell you how likely the feared event is.
The Trap of Trying to Figure Out What the Thought Means
When an intrusive thought feels significant, it is natural to start analyzing it.
You might ask yourself:
Why did I think that?
Does this mean something about me?
What if the fact that I pictured it means I could do it?
Did I feel scared enough?
What if I didn't feel scared enough?
What does it say about me that my brain went there?
Unfortunately, trying to answer these questions can make the thought even more persistent.
Your brain learns:
This thought came up, and we spent a lot of time investigating it. It must be important.
This is one reason reassurance can provide relief without actually solving the problem. You may feel better for a few minutes, but the next intrusive thought creates another question that needs an answer.
When This Feels Real” Becomes an OCD Pattern
For some women, the problem becomes less about the original intrusive thought and more about the need to feel certain about what it means.
That can lead to compulsive behaviors such as:
mentally reviewing the thought
checking your feelings or intentions
comparing yourself to other mothers
asking someone to reassure you
avoiding situations that trigger the thought
repeatedly reminding yourself that you would never hurt your baby
trying to force the thought out of your mind
These behaviors make sense when you're frightened. But they can keep the brain focused on the thought.
In OCD, the goal is often not simply to eliminate the thought. It is to stop treating the thought as a problem that must be solved.
That distinction is important.
A Thought Does Not Need to Feel Unimportant Before You Let It Go
One of the hardest things about intrusive thoughts is that people often wait to feel certain before moving on.
They may think:
“Once I know for sure that this thought doesn't mean anything, I'll be able to stop worrying about it.”
But that can keep you stuck.
You don't need to prove that a thought is meaningless before you continue with your day.
You can notice:
“My brain produced a frightening thought, and it feels important right now.”
And then return your attention to what you were doing.
The thought may still feel uncomfortable. It may still feel convincing.
That does not mean you need to investigate it.
The Goal Isn't to Make Intrusive Thoughts Disappear
Everyone has unwanted thoughts. The goal of treatment isn't to create a mind that never produces a frightening image, possibility, or “what if.”
Instead, therapy can help you change your relationship with those thoughts.
You can learn to recognize:
A thought can feel urgent without being an emergency.
A thought can feel meaningful without containing meaningful information.
A thought can be frightening without being a prediction.
And perhaps most importantly:
You do not have to feel completely certain about a thought before you let it pass.
For women experiencing postpartum OCD, this shift can be an important part of recovery.
If you're experiencing intrusive thoughts after having a baby, you may also want to read our guide to [postpartum intrusive thoughts and OCD] to learn more about what these experiences can look like and when they may be part of an OCD pattern.
If Your Thoughts Feel More Real Than You Want Them To
Feeling disturbed by an intrusive thought does not mean you secretly want it to happen. It also does not mean the thought is a prediction.
Sometimes the most frightening part is simply how convincing the thought feels.
If you find yourself spending significant time analyzing, checking, avoiding, or seeking reassurance about intrusive thoughts, therapy can help you step out of that cycle.
Red Elm Psychotherapy specializes in perinatal mental health and OCD, including postpartum intrusive thoughts and perinatal OCD. We work with women who want to feel more confident in their ability to experience uncertainty without getting pulled into endless mental checking.
About the Author
Dr. Erin Cook is a clinical psychologist and co-founder of Red Elm Psychotherapy, a Virginia-based practice specializing in perinatal mental health and OCD. She works with women navigating pregnancy, postpartum, and early motherhood, particularly when intrusive thoughts or anxiety begin to interfere with daily life.
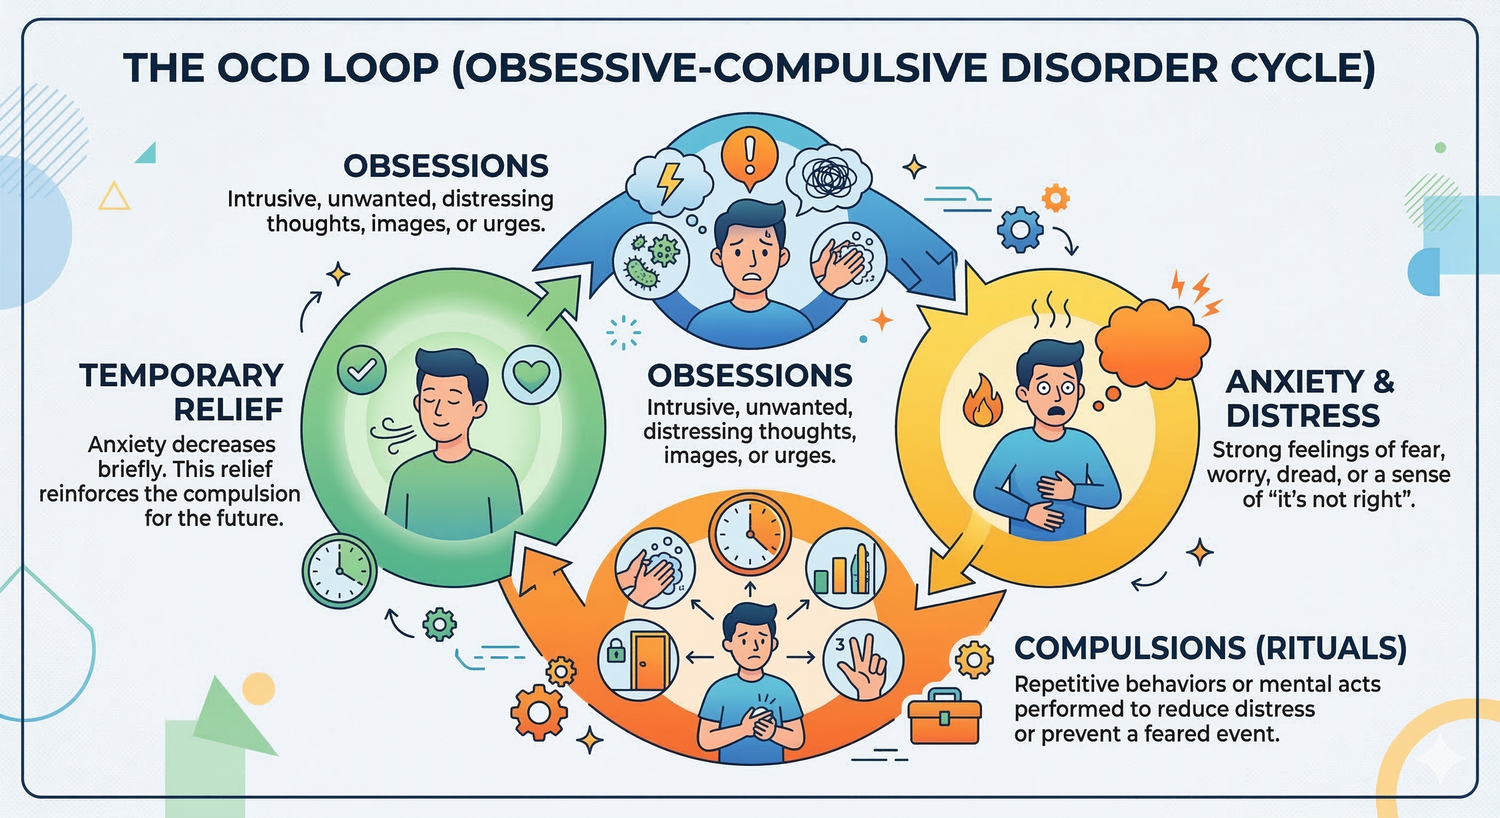
Why OCD Feels Impossible to Stop: Understanding the Obsessive-Compulsive Cycle
Obsessive-Compulsive Disorder (OCD) traps people in a cycle of intrusive thoughts, anxiety, and compulsions. Learn how the OCD cycle works and how evidence-based treatment can help break it.
At Red Elm Psychotherapy, we specialize in helping people who feel trapped in the cycle of Obsessive-Compulsive Disorder (OCD).
Many people have heard of OCD, but the reality of living with it is often misunderstood.
OCD is not simply being organized or worrying too much. It involves a cycle of unwanted thoughts, images, urges, doubts, or feelings of uncertainty—and the compulsions, avoidance, and other strategies people use to try to get relief from them.
People with OCD may recognize that their fears don't fully make sense and still find the uncertainty so distressing that it becomes incredibly difficult to resist the urge to act.
Understanding how this cycle works is the first step toward breaking it.
What is Obsessive-Compulsive Disorder?
OCD has two core components: obsessions and compulsions.
Obsessions
Obsessions are unwanted thoughts, images, urges, doubts, or sensations that create distress or uncertainty.
They can feel disturbing, out of character, or incredibly important to figure out. Even when you recognize that a thought doesn't reflect who you are, the uncertainty it creates can feel difficult to tolerate.
Compulsions
Compulsions are behaviors or mental rituals that someone feels driven to perform in an attempt to reduce distress, gain certainty, or prevent something bad from happening.
These behaviors may be visible, such as checking or washing, or internal, such as mentally reviewing memories, analyzing a thought, or repeating phrases in your mind.
Compulsions can bring temporary relief, but that relief can strengthen the OCD cycle over time.
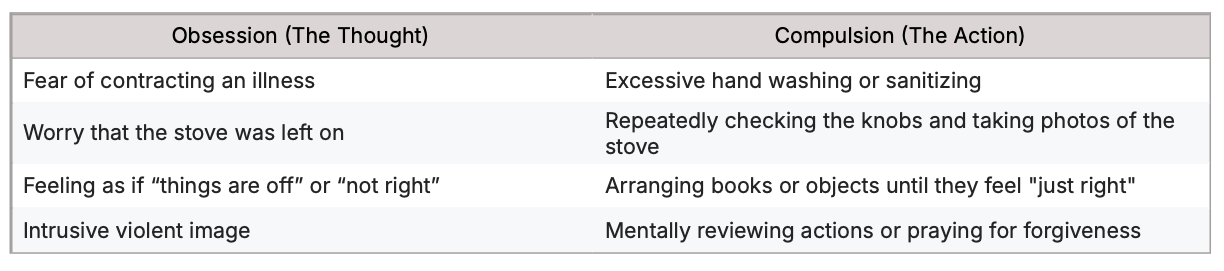
Common Examples of Obsessions and Compulsions
What Is the OCD Cycle?
At its core, the OCD cycle is a self-reinforcing pattern of uncertainty or distress, followed by an attempt to get relief, followed by temporary relief that makes the cycle stronger.
It can look something like this:
1. Trigger or uncertainty
Something happens—or simply might happen—that creates doubt, fear, discomfort, or a feeling that something isn't right.
2. Distress
The uncertainty feels difficult to tolerate. You may feel anxious, alarmed, disgusted, guilty, or compelled to figure something out.
3. Compulsion, avoidance, or reassurance
You do something to make the discomfort go away or to feel more certain. This might mean checking, washing, researching, avoiding, asking for reassurance, reviewing a memory, analyzing a thought, or performing a mental ritual.
4. Temporary relief
The distress decreases, at least for a little while. It can feel like you've finally solved the problem or prevented something bad from happening.
5. The cycle gets stronger
Because the compulsion or avoidance brought relief, your brain learns that the response was important. The next time uncertainty appears, the urge to do it again can feel even stronger.
The Reinforcement Trap
This is part of what makes OCD so difficult to stop. Compulsions work in the short term—which is exactly why they can become so powerful in the long term.
The relief teaches you to keep checking, avoiding, reassuring, analyzing, or performing rituals whenever OCD creates uncertainty or distress.
Even when you recognize that the cycle isn't logical, knowing that intellectually doesn't necessarily make it easier to stop.
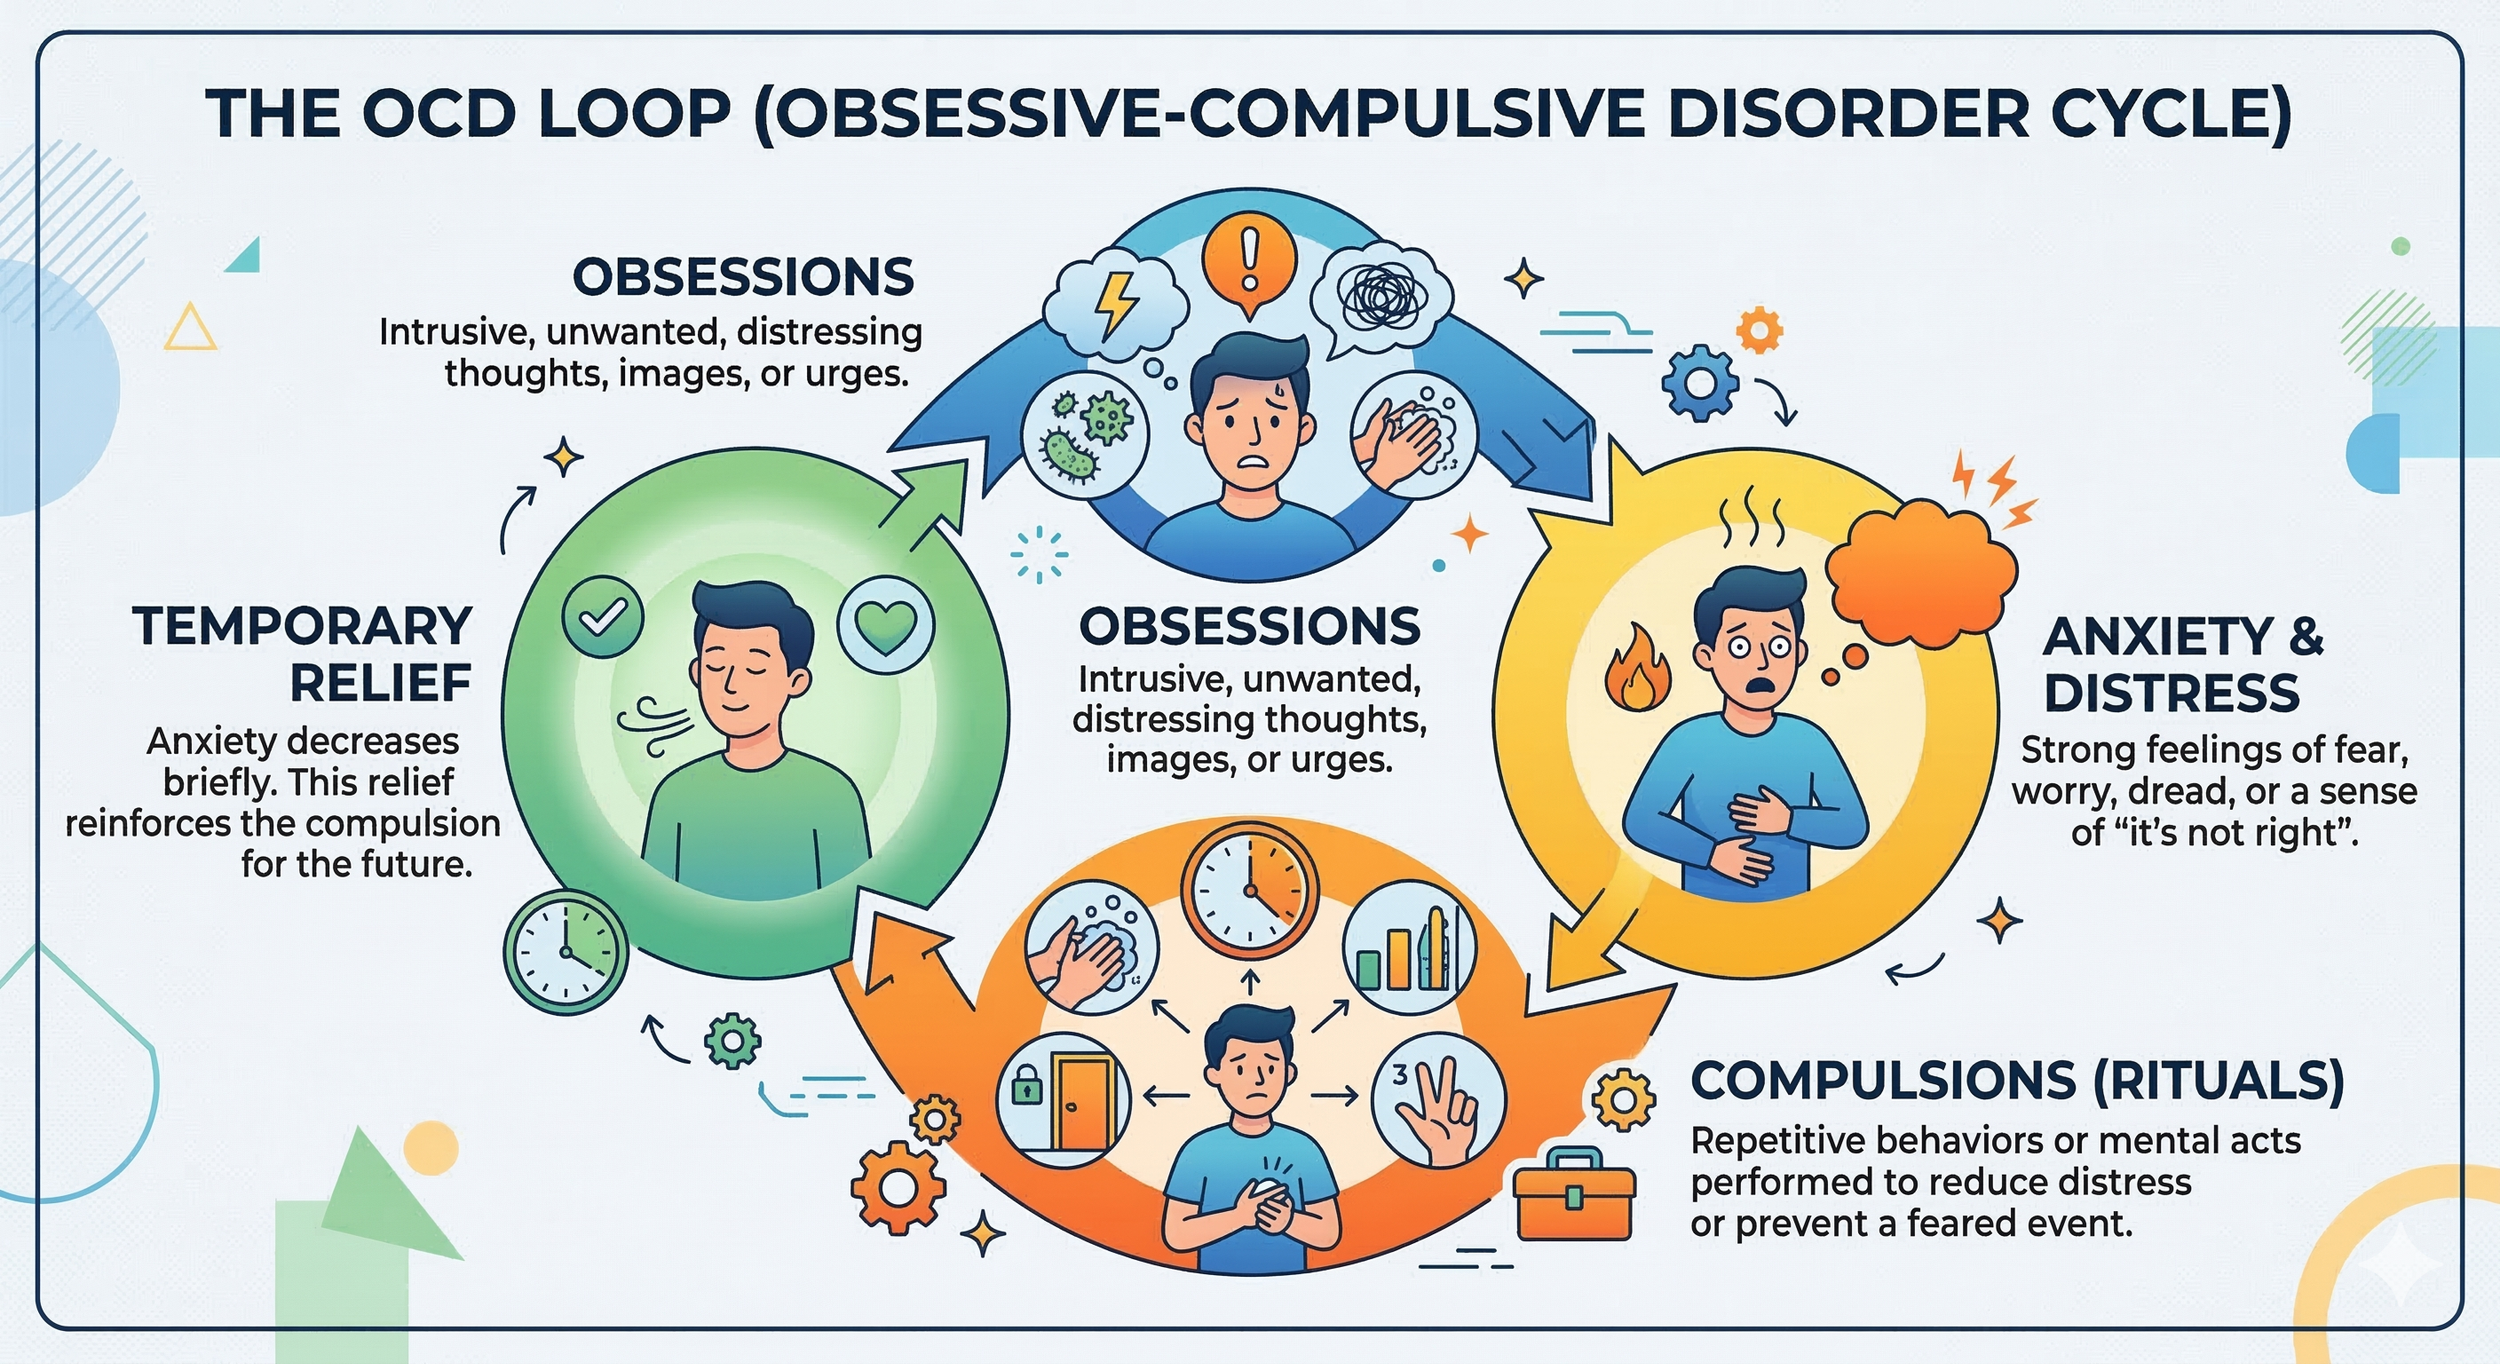
The cycle is relentless because the compulsion provides relief, which trains the brain to rely on the ritual, keeping the person trapped between their obsession and their anxiety.
Example of the OCD Cycle in Daily Life
Sarah is getting ready to leave for work when a sudden thought flashes through her mind: What if I left the stove on?
She knows she checked it before leaving the kitchen, but the uncertainty makes her uncomfortable. What if I missed something? What if the house catches fire while I'm gone?
Instead of tolerating the uncertainty, Sarah goes back to the kitchen to check the stove. She checks the burners, looks at the controls, and checks again before finally allowing herself to leave.
For a moment, she feels better. The uncertainty fades, and the anxiety drops.
But her brain has now learned that checking was important. The next time a similar doubt appears, Sarah may feel an even stronger urge to check again. Over time, she may find herself checking more often, taking longer to leave the house, or avoiding situations where she can't be completely certain that everything is safe.
The checking brought relief—but it also strengthened the cycle.
This is the pattern ERP helps interrupt: not by proving that Sarah's fear could never happen, but by helping her practice responding differently to uncertainty without automatically checking for reassurance or certainty.
Effective Treatment for OCD
The good news is that OCD is highly treatable.
One of the most effective treatments for OCD is a specialized form of cognitive behavioral therapy called Exposure and Response Prevention (ERP).
ERP helps you learn that you don't have to respond to every thought, feeling, doubt, or uncertainty with a compulsion. You can experience discomfort without automatically checking, avoiding, seeking reassurance, analyzing, or performing a ritual to make it go away.
Over time, you begin to discover that you can tolerate uncertainty and discomfort without letting OCD dictate what you do next. As this learning takes place, the cycle of OCD can begin to weaken.
About the Author
Niles Cook, PsyD, Co-Founder and Clinical Director of Red Elm Psychotherapy, is a clinical psychologist specializing in the treatment of obsessive-compulsive disorder (OCD) and anxiety disorders using Exposure and Response Prevention (ERP). He provides evidence-based OCD and anxiety treatment at Red Elm Psychotherapy in Virginia.
Ready to Take Your Life Back From OCD?
You don't have to wait until OCD gets worse to ask for help. If you're ready to understand what's keeping you stuck and explore whether ERP is right for you, we're here to help.
Schedule a consultation with Red Elm Psychotherapy to take the next step.